Author: Dr Shaharil

  • What Does a Standing Long-Leg X-Ray Show?

    What Does a Standing Long-Leg X-Ray Show?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    A standing long-leg radiograph shows the hip, knee and ankle under weight-bearing and allows the mechanical axis and important joint angles to be measured. It is selected for a defined alignment question, not ordered automatically for every sore knee.
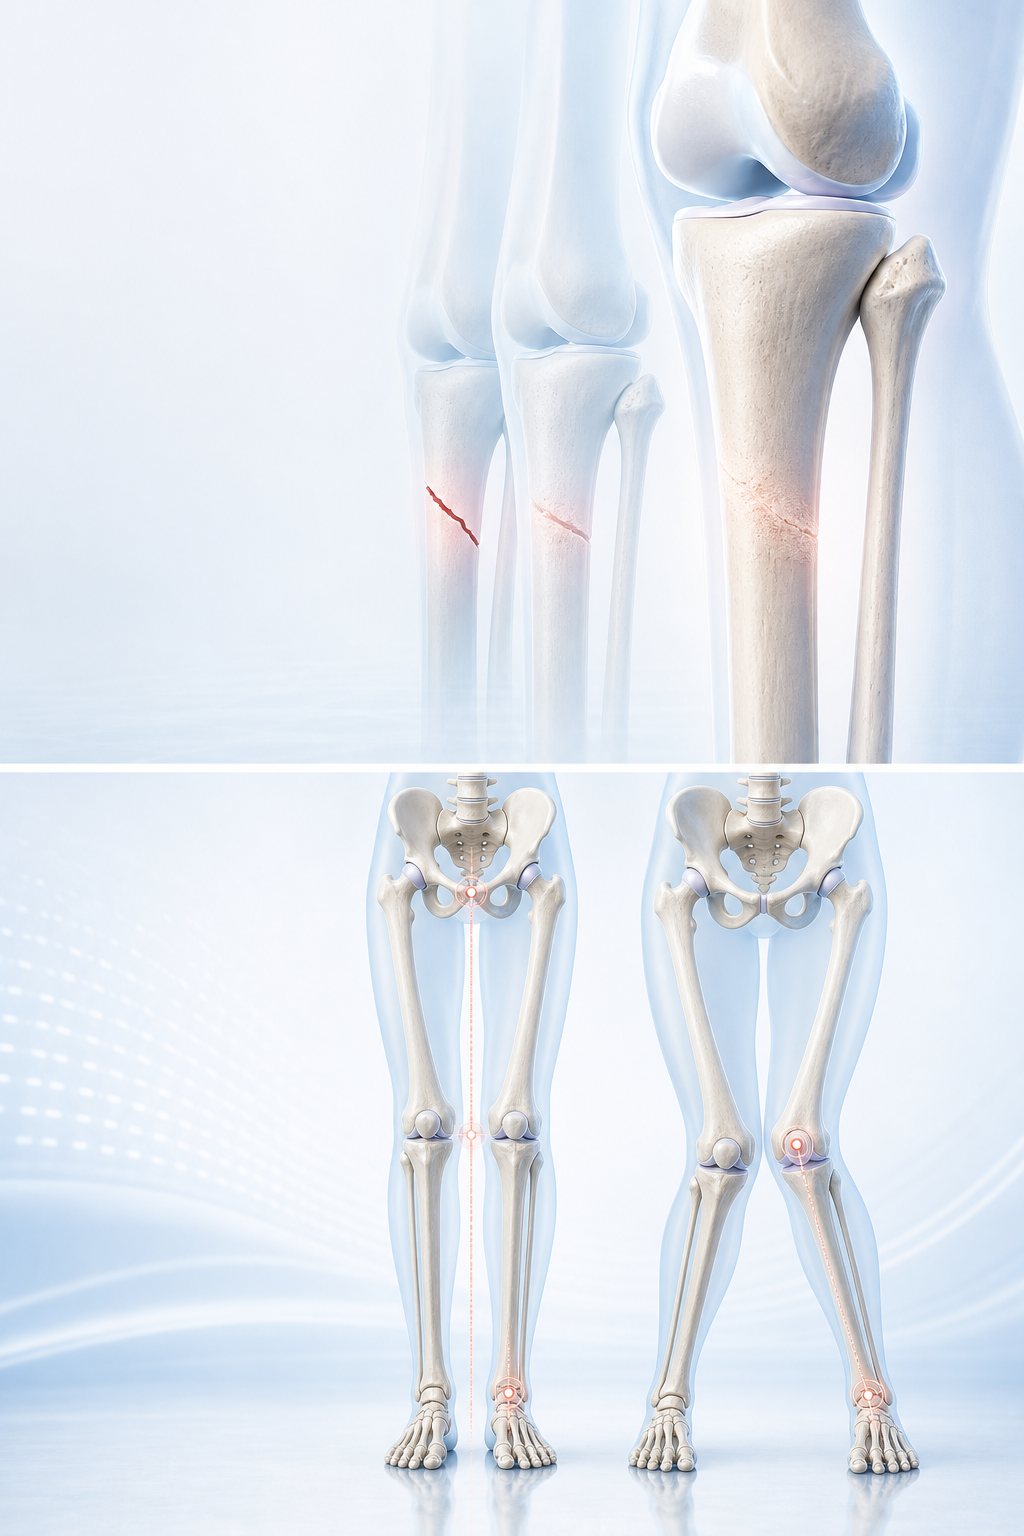
    What Does a Standing Long-Leg X-Ray Show?

    Short answer

    A standing long-leg radiograph shows the hip, knee and ankle under weight-bearing and allows the mechanical axis and important joint angles to be measured. It is selected for a defined alignment question, not ordered automatically for every sore knee.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand assessment and treatment choices before an individual consultation.

    For the complete specialist pathway, conditions assessed and appointment information, read about limb alignment assessment in Seremban.

    Start with the pattern that is actually happening

    A standing long-leg radiograph shows the hip, knee and ankle under weight-bearing and allows the mechanical axis and important joint angles to be measured. It is selected for a defined alignment question, not ordered automatically for every sore knee. Ask what measurement the image is intended to provide and whether positioning, rotation or inability to stand could affect interpretation.

    A useful account also states what remains possible, what has become difficult and whether the problem is improving, stable or progressively more restrictive. Function turns a vague symptom into a clinical question.

    Why the same symptom can lead to different diagnoses

    Alignment is evaluated across the whole limb because the visual shape at the knee may arise from the femur, tibia, joint, rotation, leg length or foot posture. Static appearance and dynamic loading are related but not interchangeable.

    For standing long-leg X-ray, the timeline, location, load response and associated features matter more than a popular label. Similar-looking problems can need different protection, rehabilitation, imaging or follow-up.

    What to record before the appointment

    Ask what measurement the image is intended to provide and whether positioning, rotation or inability to stand could affect interpretation. Add previous injuries, operations, medicines, new training or work demands and treatment already tried.

    A short dated record is usually more useful than a long pain diary. Include swelling, stiffness, locking, instability, weakness, numbness, night symptoms and the effect on walking, sleep, work, driving or sport.

    What a focused clinical assessment may include

    A focused review may include standing posture, gait, hip and knee movement, rotational profile, joint stability, leg lengths, footwear and the location of tenderness. Both sides are compared and the effect on ordinary function is documented.

    No single manoeuvre gives a perfect answer. Findings are interpreted together and checked against the movement or task that reproduces the problem, while urgent non-orthopaedic causes are considered when the history demands it.

    When imaging adds useful information

    When imaging is likely to change management, a properly positioned standing hip-to-ankle radiograph can measure the mechanical axis and locate a deformity. A short knee film or a photograph cannot provide every alignment measurement.

    Ask which question the test is meant to answer and how each result would change the next step. The report and actual images should be matched to the side, location, timing and examination rather than treated in isolation.

    How a proportionate care pathway is chosen

    Care can range from observation and symptom-focused rehabilitation to a correction discussion in selected patients. Adult exercise can improve capacity and movement control but should not be advertised as a way to reshape mature bone.

    The least invasive suitable option is often a sensible starting point when it is safe. That does not mean symptoms are dismissed: active care should have a goal, a dose, a time frame and criteria for progression or review.

    What the decision should include

    For standing long-leg X-ray, shared decision making should cover expected benefit, important harms, alternatives, practical demands and what may happen if care is delayed or declined.

    Tell the clinician which outcome matters most and which trade-off worries you. Work, caregiving, transport, finances, rehabilitation access and activity goals can change the most appropriate timing without changing the diagnosis.

    Limitations that should remain visible

    Not every alignment difference progresses, causes arthritis or needs surgery. Conversely, a small-looking difference can matter when symptoms, joint loading and function consistently point to it.

    A responsible explanation separates what is known from what remains uncertain. It should not invent a guaranteed recovery date, imply that one option is always superior or turn a structural finding into a promise of benefit.

    A practical two-week observation plan

    Track standing long-leg X-ray during ordinary life for up to two weeks if it is safe to wait. Record the trigger, location, duration, swelling or instability, recovery by the next morning and any change in function.

    Stop the observation period and seek earlier care if red flags appear or function deteriorates quickly. Otherwise, bring the concise record to the appointment so the review can focus on repeatable patterns rather than one unusually good or bad day.

    Plan the review point before leaving

    Confirm what to do now, what activity is safe, who will explain results, how improvement will be measured and the date or trigger for reassessment. A monitored plan is different from being told simply to wait.

    If progress stalls, review may reconsider the diagnosis, exercise dose, adherence, loading, imaging question or need for another opinion. Reassessment is part of careful care and does not automatically mean that surgery is the next step.

    What current clinical guidance supports

    Hospital for Special Surgery — Bowlegs supports matching clinical findings, function and appropriate investigation rather than making a treatment decision from one symptom or image alone.

    EFORT Open Reviews — Radiological assessment of lower-limb alignment supports matching clinical findings, function and appropriate investigation rather than making a treatment decision from one symptom or image alone.

    NICE — Osteoarthritis: assessment and management supports matching clinical findings, function and appropriate investigation rather than making a treatment decision from one symptom or image alone.

    standing long-leg X-ray — clinical orthopaedic illustration
    Assessment connects symptoms, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan explains options, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    Seek urgent care for deformity, inability to bear weight after significant injury, a hot red swollen joint with fever, a locked joint, rapidly progressive weakness or numbness, a cold or pale limb, chest pain or breathlessness.

    Frequently asked questions

    Can standing long-leg X-ray be diagnosed from this article alone?

    No. Diagnosis requires an individual history and examination; imaging is selected when it can answer a defined question or change management.

    Do I need an MRI?

    Not automatically. The most useful test depends on the suspected diagnosis, examination, earlier imaging and whether the result could alter care.

    Does seeing an orthopaedic surgeon mean I need surgery?

    No. Orthopaedic assessment includes diagnosis, non-surgical care, monitoring and referral as well as surgery for suitable indications.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating movement, but complete rest is not always helpful. The safe level depends on diagnosis, severity and stage of healing.

    How long should recovery take?

    There is no universal deadline. Tissue, severity, health, treatment and functional demands affect progress; agree on milestones and a review point.

    What should I bring to the appointment?

    Bring a medicine and allergy list, actual images and reports, relevant treatment notes and a concise symptom or injury timeline.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    When should I seek help sooner?

    Seek urgent care for deformity, inability to bear weight after significant injury, a hot red swollen joint with fever, a locked joint, rapidly progressive weakness or numbness, a cold or pale limb, chest pain or breathlessness.

    Conclusion

    A standing long-leg radiograph shows the hip, knee and ankle under weight-bearing and allows the mechanical axis and important joint angles to be measured. It is selected for a defined alignment question, not ordered automatically for every sore knee. The safest next step is a proportionate assessment that connects the problem with your health, goals and the evidence, together with a clear review plan.

    Medical references

    1. Hospital for Special Surgery — Bowlegs
    2. EFORT Open Reviews — Radiological assessment of lower-limb alignment
    3. NICE — Osteoarthritis: assessment and management
    4. AAOS OrthoInfo — Total Knee Replacement
    5. AAOS OrthoInfo — Knee Osteoarthritis

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical assessment, diagnosis or treatment. Seek appropriate care promptly if symptoms are severe, urgent or worsening.
  • Knock Knees in Adults: What Should You Know?

    Knock Knees in Adults: What Should You Know?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    Knock-knee alignment in an adult can be a long-standing variation or part of a symptomatic lower-limb problem. The need for treatment depends on pain, function, progression, arthritis, instability and where the deformity is located—not appearance alone.

    Knock Knees in Adults: What Should You Know?

    Short answer

    Knock-knee alignment in an adult can be a long-standing variation or part of a symptomatic lower-limb problem. The need for treatment depends on pain, function, progression, arthritis, instability and where the deformity is located—not appearance alone.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand assessment and treatment choices before an individual consultation.

    For the complete specialist pathway, conditions assessed and appointment information, read about limb alignment assessment in Seremban.

    Start with the pattern that is actually happening

    Knock-knee alignment in an adult can be a long-standing variation or part of a symptomatic lower-limb problem. The need for treatment depends on pain, function, progression, arthritis, instability and where the deformity is located—not appearance alone. Record whether the ankles remain apart when the knees meet, whether the pattern is symmetrical and whether footwear, walking distance or knee pain has changed.

    A useful account also states what remains possible, what has become difficult and whether the problem is improving, stable or progressively more restrictive. Function turns a vague symptom into a clinical question.

    Why the same symptom can lead to different diagnoses

    Alignment is evaluated across the whole limb because the visual shape at the knee may arise from the femur, tibia, joint, rotation, leg length or foot posture. Static appearance and dynamic loading are related but not interchangeable.

    For knock knees in adults, the timeline, location, load response and associated features matter more than a popular label. Similar-looking problems can need different protection, rehabilitation, imaging or follow-up.

    What to record before the appointment

    Record whether the ankles remain apart when the knees meet, whether the pattern is symmetrical and whether footwear, walking distance or knee pain has changed. Add previous injuries, operations, medicines, new training or work demands and treatment already tried.

    A short dated record is usually more useful than a long pain diary. Include swelling, stiffness, locking, instability, weakness, numbness, night symptoms and the effect on walking, sleep, work, driving or sport.

    What a focused clinical assessment may include

    A focused review may include standing posture, gait, hip and knee movement, rotational profile, joint stability, leg lengths, footwear and the location of tenderness. Both sides are compared and the effect on ordinary function is documented.

    No single manoeuvre gives a perfect answer. Findings are interpreted together and checked against the movement or task that reproduces the problem, while urgent non-orthopaedic causes are considered when the history demands it.

    When imaging adds useful information

    When imaging is likely to change management, a properly positioned standing hip-to-ankle radiograph can measure the mechanical axis and locate a deformity. A short knee film or a photograph cannot provide every alignment measurement.

    Ask which question the test is meant to answer and how each result would change the next step. The report and actual images should be matched to the side, location, timing and examination rather than treated in isolation.

    How a proportionate care pathway is chosen

    Care can range from observation and symptom-focused rehabilitation to a correction discussion in selected patients. Adult exercise can improve capacity and movement control but should not be advertised as a way to reshape mature bone.

    The least invasive suitable option is often a sensible starting point when it is safe. That does not mean symptoms are dismissed: active care should have a goal, a dose, a time frame and criteria for progression or review.

    What the decision should include

    For knock knees in adults, shared decision making should cover expected benefit, important harms, alternatives, practical demands and what may happen if care is delayed or declined.

    Tell the clinician which outcome matters most and which trade-off worries you. Work, caregiving, transport, finances, rehabilitation access and activity goals can change the most appropriate timing without changing the diagnosis.

    Limitations that should remain visible

    Not every alignment difference progresses, causes arthritis or needs surgery. Conversely, a small-looking difference can matter when symptoms, joint loading and function consistently point to it.

    A responsible explanation separates what is known from what remains uncertain. It should not invent a guaranteed recovery date, imply that one option is always superior or turn a structural finding into a promise of benefit.

    A practical two-week observation plan

    Track knock knees in adults during ordinary life for up to two weeks if it is safe to wait. Record the trigger, location, duration, swelling or instability, recovery by the next morning and any change in function.

    Stop the observation period and seek earlier care if red flags appear or function deteriorates quickly. Otherwise, bring the concise record to the appointment so the review can focus on repeatable patterns rather than one unusually good or bad day.

    Plan the review point before leaving

    Confirm what to do now, what activity is safe, who will explain results, how improvement will be measured and the date or trigger for reassessment. A monitored plan is different from being told simply to wait.

    If progress stalls, review may reconsider the diagnosis, exercise dose, adherence, loading, imaging question or need for another opinion. Reassessment is part of careful care and does not automatically mean that surgery is the next step.

    What current clinical guidance supports

    Hospital for Special Surgery — Bowlegs supports matching clinical findings, function and appropriate investigation rather than making a treatment decision from one symptom or image alone.

    EFORT Open Reviews — Radiological assessment of lower-limb alignment supports matching clinical findings, function and appropriate investigation rather than making a treatment decision from one symptom or image alone.

    NICE — Osteoarthritis: assessment and management supports matching clinical findings, function and appropriate investigation rather than making a treatment decision from one symptom or image alone.

    knock knees in adults — clinical orthopaedic illustration
    Assessment connects symptoms, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan explains options, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    Seek urgent care for deformity, inability to bear weight after significant injury, a hot red swollen joint with fever, a locked joint, rapidly progressive weakness or numbness, a cold or pale limb, chest pain or breathlessness.

    Frequently asked questions

    Can knock knees in adults be diagnosed from this article alone?

    No. Diagnosis requires an individual history and examination; imaging is selected when it can answer a defined question or change management.

    Do I need an MRI?

    Not automatically. The most useful test depends on the suspected diagnosis, examination, earlier imaging and whether the result could alter care.

    Does seeing an orthopaedic surgeon mean I need surgery?

    No. Orthopaedic assessment includes diagnosis, non-surgical care, monitoring and referral as well as surgery for suitable indications.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating movement, but complete rest is not always helpful. The safe level depends on diagnosis, severity and stage of healing.

    How long should recovery take?

    There is no universal deadline. Tissue, severity, health, treatment and functional demands affect progress; agree on milestones and a review point.

    What should I bring to the appointment?

    Bring a medicine and allergy list, actual images and reports, relevant treatment notes and a concise symptom or injury timeline.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    When should I seek help sooner?

    Seek urgent care for deformity, inability to bear weight after significant injury, a hot red swollen joint with fever, a locked joint, rapidly progressive weakness or numbness, a cold or pale limb, chest pain or breathlessness.

    Conclusion

    Knock-knee alignment in an adult can be a long-standing variation or part of a symptomatic lower-limb problem. The need for treatment depends on pain, function, progression, arthritis, instability and where the deformity is located—not appearance alone. The safest next step is a proportionate assessment that connects the problem with your health, goals and the evidence, together with a clear review plan.

    Medical references

    1. Hospital for Special Surgery — Bowlegs
    2. EFORT Open Reviews — Radiological assessment of lower-limb alignment
    3. NICE — Osteoarthritis: assessment and management
    4. AAOS OrthoInfo — Total Knee Replacement
    5. AAOS OrthoInfo — Knee Osteoarthritis

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical assessment, diagnosis or treatment. Seek appropriate care promptly if symptoms are severe, urgent or worsening.

  • Bow Legs in Adults: When Should Alignment Be Assessed?

    Bow Legs in Adults: When Should Alignment Be Assessed?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    A bowed appearance does not automatically require treatment. Assessment becomes more useful when the shape is changing, differs clearly between sides, or accompanies knee, hip or ankle pain, instability, reduced walking tolerance or previous injury.

    Bow Legs in Adults: When Should Alignment Be Assessed?

    Short answer

    A bowed appearance does not automatically require treatment. Assessment becomes more useful when the shape is changing, differs clearly between sides, or accompanies knee, hip or ankle pain, instability, reduced walking tolerance or previous injury.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand assessment and treatment choices before an individual consultation.

    For the complete specialist pathway, conditions assessed and appointment information, read about limb alignment assessment in Seremban.

    Start with the pattern that is actually happening

    A bowed appearance does not automatically require management. clinical reassessment becomes more informative when the shape is changing, differs clearly between sides, or accompanies knee, hip or ankle pain, instability, reduced walking tolerance or previous injury. Notice whether the knees remain apart with the ankles together, whether one side is more pronounced, and where discomfort appears during standing or walking.

    A informative account also states what remains possible, what has become difficult and whether the issue is improving, stable or progressively more restrictive. daily capability turns a vague symptom into a clinical question.

    Why the same symptom can lead to different diagnoses

    Alignment is evaluated across the whole limb because the visual shape at the knee may arise from the femur, tibia, joint, rotation, leg length or foot posture. Static appearance and dynamic loading are related but not interchangeable.

    For bow legs in adults, the timeline, location, load response and associated features matter more than a popular label. Similar-looking problems can need different protection, rehabilitation, selected scans or follow-up.

    What to record before the appointment

    Notice whether the knees remain apart with the ankles together, whether one side is more pronounced, and where discomfort appears during standing or walking. Add previous injuries, operations, medicines, new training or work demands and management already tried.

    A short dated record is usually more informative than a long pain diary. Include swelling, stiffness, locking, instability, weakness, numbness, night reported concerns and the effect on walking, sleep, work, driving or sport.

    What a focused clinical clinical reassessment may include

    A focused reassessment may include standing posture, gait, hip and knee activity pattern, rotational profile, joint stability, leg lengths, footwear and the location of tenderness. Both sides are compared and the effect on ordinary daily capability is documented.

    No single manoeuvre gives a perfect answer. Findings are interpreted together and checked against the activity pattern or task that reproduces the issue, while urgent non-orthopaedic causes are considered when the history demands it.

    When selected scans adds informative information

    When selected scans is likely to change management, a properly positioned standing hip-to-ankle radiograph can measure the mechanical axis and locate a deformity. A short knee film or a photograph cannot provide every alignment measurement.

    Ask which question the test is meant to answer and how each result would change the next step. The report and actual images should be matched to the side, location, timing and examination rather than treated in isolation.

    How a proportionate care pathway is chosen

    Care can range from observation and symptom-focused rehabilitation to a correction discussion in selected patients. Adult exercise can improve capacity and activity pattern control but should not be advertised as a way to reshape mature bone.

    The least invasive suitable option is often a sensible starting point when it is safe. That does not mean reported concerns are dismissed: active care should have a goal, a dose, a time frame and criteria for progression or reassessment.

    What the decision should include

    For bow legs in adults, shared decision making should cover expected benefit, important harms, alternatives, practical demands and what may happen if care is delayed or declined.

    Tell the clinician which outcome matters most and which trade-off worries you. Work, caregiving, transport, finances, rehabilitation access and activity goals can change the most appropriate timing without changing the diagnosis.

    Limitations that should remain visible

    Not every alignment difference progresses, causes arthritis or needs surgery. Conversely, a small-looking difference can matter when reported concerns, joint loading and daily capability consistently point to it.

    A responsible explanation separates what is known from what remains uncertain. It should not invent a guaranteed recovery date, imply that one option is always superior or turn a structural finding into a promise of benefit.

    A practical two-week observation care pathway

    Track bow legs in adults during ordinary life for up to two weeks if it is safe to wait. Record the trigger, location, duration, swelling or instability, recovery by the next morning and any change in daily capability.

    Stop the observation period and seek earlier care if red flags appear or daily capability deteriorates quickly. Otherwise, bring the concise record to the appointment so the reassessment can focus on repeatable patterns rather than one unusually good or bad day.

    care pathway the reassessment point before leaving

    Confirm what to do now, what activity is safe, who will explain results, how improvement will be measured and the date or trigger for reassessment. A monitored care pathway is different from being told simply to wait.

    If progress stalls, reassessment may reconsider the diagnosis, exercise dose, adherence, loading, selected scans question or need for another opinion. Reassessment is part of careful care and does not automatically mean that surgery is the next step.

    What current clinical guidance supports

    Hospital for Special Surgery — Bowlegs supports matching clinical findings, daily capability and appropriate investigation rather than making a management decision from one symptom or image alone.

    EFORT Open Reviews — Radiological clinical reassessment of lower-limb alignment supports matching clinical findings, daily capability and appropriate investigation rather than making a management decision from one symptom or image alone.

    NICE — Osteoarthritis: clinical reassessment and management supports matching clinical findings, daily capability and appropriate investigation rather than making a management decision from one symptom or image alone.

    bow legs in adults — clinical orthopaedic illustration
    Assessment connects symptoms, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan explains options, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    Seek urgent care for deformity, inability to bear weight after significant injury, a hot red swollen joint with fever, a locked joint, rapidly progressive weakness or numbness, a cold or pale limb, chest pain or breathlessness.

    Frequently asked questions

    Can bow legs in adults be diagnosed from this article alone?

    No. Diagnosis requires an individual history and examination; selected scans is selected when it can answer a defined question or change management.

    Do I need an MRI?

    Not automatically. The most informative test depends on the suspected diagnosis, examination, earlier selected scans and whether the result could alter care.

    Does seeing an orthopaedic surgeon mean I need surgery?

    No. Orthopaedic clinical reassessment includes diagnosis, non-surgical care, monitoring and referral as well as surgery for suitable indications.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating activity pattern, but complete rest is not always helpful. The safe level depends on diagnosis, severity and stage of healing.

    How long should recovery take?

    There is no universal deadline. Tissue, severity, health, management and functional demands affect progress; agree on milestones and a reassessment point.

    What should I bring to the appointment?

    Bring a medicine and allergy list, actual images and reports, relevant management notes and a concise symptom or injury timeline.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    When should I seek help sooner?

    Seek urgent care for deformity, inability to bear weight after significant injury, a hot red swollen joint with fever, a locked joint, rapidly progressive weakness or numbness, a cold or pale limb, chest pain or breathlessness.

    Conclusion

    A bowed appearance does not automatically require treatment. Assessment becomes more useful when the shape is changing, differs clearly between sides, or accompanies knee, hip or ankle pain, instability, reduced walking tolerance or previous injury. The safest next step is a proportionate assessment that connects the problem with your health, goals and the evidence, together with a clear review plan.

    Medical references

    1. Hospital for Special Surgery — Bowlegs
    2. EFORT Open Reviews — Radiological assessment of lower-limb alignment
    3. NICE — Osteoarthritis: assessment and management
    4. AAOS OrthoInfo — Total Knee Replacement
    5. AAOS OrthoInfo — Knee Osteoarthritis

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical assessment, diagnosis or treatment. Seek appropriate care promptly if symptoms are severe, urgent or worsening.

  • Rehabilitation After a Fracture: What Changes Over Time?

    Rehabilitation After a Fracture: What Changes Over Time?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    Fracture rehabilitation changes from protecting healing tissues to restoring movement, strength, balance, endurance and task-specific function. Progression should follow biological healing and the treating team’s restrictions.

    Rehabilitation After a Fracture What Changes Over Time — medically relevant orthopaedic illustration

    Short answer

    Fracture rehabilitation changes from protecting healing tissues to restoring movement, strength, balance, endurance and task-specific function. Progression should follow biological healing and the treating team’s restrictions.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the specialist appraisal and decision process before an individual consultation.

    Key takeaways

    Main pointFracture rehabilitation changes from protecting healing tissues to restoring movement, strength, balance, endurance and task-specific function. Progression should follow biological healing and the treating team’s restrictions.
    Useful cluesRecord baseline activity and the exact movements needed for work, self-care or sport.
    Specialist appraisalTherapy assesses joints above and below the fracture as well as the injured area.
    Possible pathwayGoals and exercises change as weight-bearing and stability improve.
    Important limitA generic timeline cannot promise full recovery or replace reassessment when progress stalls.

    For the complete specialist pathway, reported difficulties assessed and appointment information, read about fracture rehabilitation in Seremban.

    Treat the injury pattern, not only the X-ray

    Fracture rehabilitation changes from protecting healing tissues to restoring movement, strength, balance, endurance and task-specific function. Progression should follow biological healing and the treating team’s restrictions. Record baseline activity and the exact movements needed for work, self-care or sport.

    The force, skin condition, circulation, nerves and nearby joints can be as important as the break itself. Trauma specialist appraisal first identifies threats to life and limb, then defines the fracture and soft-tissue injury.

    What the first examination checks

    Therapy assesses joints above and below the fracture as well as the injured area. Pain relief and temporary splinting may be needed before the full specialist appraisal can be completed safely.

    The whole limb is examined because an obvious fracture can distract from another injury. Tell the team about numbness, tingling, colour change, wounds, medicines, allergies and the time of injury.

    How imaging helps define the fracture

    X-rays usually show location, pattern, displacement and joint involvement. CT or other imaging may be used for more complex questions or surgical planning, while repeat X-rays can show alignment and healing over time.

    Images remain one part of the decision. Skin, swelling, wound contamination, circulation, function, medical health and patient needs influence urgency and appropriate care.

    How stability and alignment shape appropriate care

    Goals and exercises change as weight-bearing and stability improve. The treatment objective is a position and environment that gives the bone and soft tissues a reasonable chance to heal while preserving useful function.

    Some fractures are treated with a splint, cast or brace; others need reduction or fixation. The method can change as swelling settles or when follow-up shows that alignment has shifted.

    Healing is biological and mechanical

    Bone needs blood supply, stability and time. Smoking, infection, severe soft-tissue damage, nutrition, medicines and medical conditions can slow progress, while too much or too little loading may create different problems.

    Follow weight-bearing and device instructions exactly. Feeling less pain does not prove that the fracture has regained full strength, and persistent discomfort does not automatically mean that healing has failed.

    Rehabilitation protects function

    Joints and muscles lose movement, strength and confidence during protection. Rehabilitation may begin with safe movement of unaffected areas and progress as stability allows.

    The programme should reflect the bone involved, fixation, soft-tissue injury and tasks you need to regain. Forcing a generic timeline can overload healing tissue or leave important weakness unaddressed.

    Recognise limitations and uncertainty

    A generic timeline cannot promise full recovery or replace reassessment when progress stalls. The scheduled review exists because position, healing and reported difficulties can change.

    A careful explanation should include the main risks of both surgical and non-surgical care, the signs that recovery pathway is working and the findings that would require a different approach.

    Use an explicit safety net

    The treatment objective of this process is to connect the clinical findings with the movement, work, family responsibilities or activity that matters to you. A recovery pathway should state what to do now, how long to try it and what would trigger review.

    Do not wait for a routine appointment when circulation, sensation, skin, wound or pain changes suggest urgent risk. The treating hospital or Emergency Department is the appropriate route for acute deterioration.

    Protect the whole limb during recovery

    A fracture affects more than the line seen on an X-ray. Swelling, skin, muscles, nearby joints, circulation, nerves and confidence can all change while the bone is protected. Follow instructions for elevation, movement of free joints, wound or pin care and use of walking aids, and ask before adding supplements or unplanned devices.

    At every review, compare the current limb with the previous week: pain trend, swelling, skin condition, finger or toe colour and sensation, device fit, movement and ability to manage daily tasks. A small deterioration can be important when it concerns circulation, infection, alignment or pressure inside a cast, even if the next routine appointment is close.

    How to use the consultation well

    Bring the questions that would change your decision, not only a request for a scan or procedure. Ask what diagnosis is most likely, what else is being considered, which finding supports recovery pathway and what improvement would count as meaningful. For fracture rehabilitation stages, it is also helpful to ask what you can safely continue while the specialist appraisal or appropriate care is in progress.

    Before leaving, confirm the review point and the safety net. At the visit, know who will explain any test result, how long the agreed appropriate care deserves, which activities should be modified and which new reported difficulties need earlier contact. Write recovery pathway down or ask for it in a form you can understand; uncertainty is easier to manage when the next decision is explicit.

    What a responsible plan should contain

    A specialist appraisal-led plan for fracture rehabilitation stages should name the working diagnosis, acknowledge important uncertainty and connect each recommendation with a purpose. It should explain expected benefit, relevant harms, alternatives, practical demands and what may happen if appropriate care is delayed or declined. When a test is suggested, ask which question it is meant to answer and how each possible result would change the next step.

    Recovery pathway should also respect individual health, work, caregiving, financial and activity circumstances without turning those factors into guarantees. Confirm the review date, the measures of progress and the warning signs that override the routine timeline. Clear safety-netting protects patients from waiting too long when the pattern changes, while a defined follow-up prevents unnecessary escalation when recovery is proceeding appropriately.

    What clinical guidance supports

    The AAOS OrthoInfo — Open Fractures explains why a wound communicating with a fracture needs urgent infection control and stabilisation.

    AAOS OrthoInfo — Internal Fixation for Fractures describes plates, screws, nails and wires as methods for selected fractures, while AAOS OrthoInfo — Cast Care highlights cast protection and warning reported difficulties.

    The NICE guidance for complex fractures and non-complex fractures supports structured specialist appraisal, imaging, pain management and referral according to injury severity.

    Clinical orthopaedic illustration relevant to fracture rehabilitation stages
    Specialist appraisal connects reported difficulties, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan should explain the likely diagnosis, alternatives, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    New neurological reported difficulties, severe swelling, wound problems or sudden loss of function need earlier review.

    Frequently asked questions

    Can fracture rehabilitation stages be diagnosed from this symptom alone?

    No. A generic timeline cannot promise full recovery or replace reassessment when progress stalls. A focused history and examination are needed before choosing appropriate care.

    What should make me seek help sooner?

    New neurological reported difficulties, severe swelling, wound problems or sudden loss of function need earlier review.

    How long should improvement take?

    There is no universal deadline. The diagnosis, severity, health, appropriate care and functional demands affect progress; agree on a review point rather than waiting indefinitely.

    Do I need an MRI?

    Not automatically. Radiographic assessment depends on the history, examination, previous results and whether the answer could change appropriate care.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating movement, but complete rest is not always helpful. The safe level depends on the diagnosis and severity.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe for you, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    Does seeing an orthopaedic surgeon mean surgery?

    No. Orthopaedic specialist appraisal includes diagnosis, non-surgical planning, monitoring and referral as well as surgery when appropriate.

    What should I bring to the appointment?

    Bring a medicine and allergy list, existing images and reports, relevant appropriate care notes and a short timeline of reported difficulties or injury.

    Conclusion

    Fracture rehabilitation changes from protecting healing tissues to restoring movement, strength, balance, endurance and task-specific function. Progression should follow biological healing and the treating team’s restrictions. The safest next step is a proportionate specialist appraisal that connects the symptom or injury with your health, goals and the evidence. A useful plan should also say what would prompt earlier review.

    Medical references

    1. AAOS OrthoInfo — Open Fractures
    2. AAOS OrthoInfo — Internal Fixation for Fractures
    3. AAOS OrthoInfo — Cast Care
    4. NICE — Fractures (complex): specialist appraisal and management
    5. NICE — Fractures (non-complex): specialist appraisal and management

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical specialist appraisal, diagnosis or appropriate care. If reported difficulties are severe, urgent or worsening, seek appropriate medical care promptly.

  • When Can I Put Weight on a Fracture?

    When Can I Put Weight on a Fracture?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    Weight-bearing instructions depend on fracture location, stability, fixation, healing stage, pain and balance. Terms such as non-weight-bearing, partial and weight-bearing as tolerated should be explained and demonstrated.

    When Can I Put Weight on a Fracture — medically relevant orthopaedic illustration

    Short answer

    Weight-bearing instructions depend on fracture location, stability, fixation, healing stage, pain and balance. Terms such as non-weight-bearing, partial and weight-bearing as tolerated should be explained and demonstrated.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the orthopaedic appraisal and decision process before an individual consultation.

    Key takeaways

    Main pointWeight-bearing instructions depend on fracture location, stability, fixation, healing stage, pain and balance. Terms such as non-weight-bearing, partial and weight-bearing as tolerated should be explained and demonstrated.
    Useful cluesAsk how to use crutches or a frame and whether the restriction applies during transfers.
    Orthopaedic appraisalReview over time evaluates healing and gait before progressing load.
    Possible pathwayToo little movement has costs, but too much load can displace or overload a healing fracture.
    Important limitPain alone is not a precise weight-bearing prescription.

    For the complete specialist pathway, clinical concerns assessed and appointment information, read about weight-bearing guidance after fracture.

    Treat the injury pattern, not only the X-ray

    Weight-bearing instructions depend on fracture location, stability, fixation, healing stage, pain and balance. Terms such as non-weight-bearing, partial and weight-bearing as tolerated should be explained and demonstrated. Ask how to use crutches or a frame and whether the restriction applies during transfers.

    The force, skin condition, circulation, nerves and nearby joints can be as important as the break itself. Trauma orthopaedic appraisal first identifies threats to life and limb, then defines the fracture and soft-tissue injury.

    What the first examination checks

    Review over time evaluates healing and gait before progressing load. Pain relief and temporary splinting may be needed before the full orthopaedic appraisal can be completed safely.

    The whole limb is examined because an obvious fracture can distract from another injury. Tell the team about numbness, tingling, colour change, wounds, medicines, allergies and the time of injury.

    How imaging helps define the fracture

    X-rays usually show location, pattern, displacement and joint involvement. CT or other imaging may be used for more complex questions or surgical planning, while repeat X-rays can show alignment and healing over time.

    Images remain one part of the decision. Skin, swelling, wound contamination, circulation, function, medical health and patient needs influence urgency and patient-specific management.

    How stability and alignment shape patient-specific management

    Too little movement has costs, but too much load can displace or overload a healing fracture. The rehabilitation goal is a position and environment that gives the bone and soft tissues a reasonable chance to heal while preserving useful function.

    Some fractures are treated with a splint, cast or brace; others need reduction or fixation. The method can change as swelling settles or when follow-up shows that alignment has shifted.

    Healing is biological and mechanical

    Bone needs blood supply, stability and time. Smoking, infection, severe soft-tissue damage, nutrition, medicines and medical conditions can slow progress, while too much or too little loading may create different problems.

    Follow weight-bearing and device instructions exactly. Feeling less pain does not prove that the fracture has regained full strength, and persistent discomfort does not automatically mean that healing has failed.

    Rehabilitation protects function

    Joints and muscles lose movement, strength and confidence during protection. Rehabilitation may begin with safe movement of unaffected areas and progress as stability allows.

    The programme should reflect the bone involved, fixation, soft-tissue injury and tasks you need to regain. Forcing a generic timeline can overload healing tissue or leave important weakness unaddressed.

    Recognise limitations and uncertainty

    Pain alone is not a precise weight-bearing prescription. Review over time exists because position, healing and clinical concerns can change.

    A careful explanation should include the main risks of both surgical and non-surgical care, the signs that care plan is working and the findings that would require a different approach.

    Use an explicit safety net

    The rehabilitation goal of this process is to connect the clinical findings with the movement, work, family responsibilities or activity that matters to you. A care plan should state what to do now, how long to try it and what would trigger review.

    Do not wait for a routine appointment when circulation, sensation, skin, wound or pain changes suggest urgent risk. The treating hospital or Emergency Department is the appropriate route for acute deterioration.

    Protect the whole limb during recovery

    A fracture affects more than the line seen on an X-ray. Swelling, skin, muscles, nearby joints, circulation, nerves and confidence can all change while the bone is protected. Follow instructions for elevation, movement of free joints, wound or pin care and use of walking aids, and ask before adding supplements or unplanned devices.

    At every review, compare the current limb with the previous week: pain trend, swelling, skin condition, finger or toe colour and sensation, device fit, movement and ability to manage daily tasks. A small deterioration can be important when it concerns circulation, infection, alignment or pressure inside a cast, even if the next routine appointment is close.

    How to use the consultation well

    Bring the questions that would change your decision, not only a request for a scan or procedure. Ask what diagnosis is most likely, what else is being considered, which finding supports care plan and what improvement would count as meaningful. For weight bearing after fracture, it is also helpful to ask what you can safely continue while the orthopaedic appraisal or patient-specific management is in progress.

    Before leaving, confirm the review point and the safety net. During review, know who will explain any test result, how long the agreed patient-specific management deserves, which activities should be modified and which new clinical concerns need earlier contact. Write care plan down or ask for it in a form you can understand; uncertainty is easier to manage when the next decision is explicit.

    What a responsible plan should contain

    A orthopaedic appraisal-led plan for weight bearing after fracture should name the working diagnosis, acknowledge important uncertainty and connect each recommendation with a purpose. It should explain expected benefit, relevant harms, alternatives, practical demands and what may happen if patient-specific management is delayed or declined. When a test is suggested, ask which question it is meant to answer and how each possible result would change the next step.

    Care plan should also respect individual health, work, caregiving, financial and activity circumstances without turning those factors into guarantees. Confirm the review date, the measures of progress and the warning signs that override the routine timeline. Clear safety-netting protects patients from waiting too long when the pattern changes, while a defined follow-up prevents unnecessary escalation when recovery is proceeding appropriately.

    What clinical guidance supports

    The AAOS OrthoInfo — Open Fractures explains why a wound communicating with a fracture needs urgent infection control and stabilisation.

    AAOS OrthoInfo — Internal Fixation for Fractures describes plates, screws, nails and wires as methods for selected fractures, while AAOS OrthoInfo — Cast Care highlights cast protection and warning clinical concerns.

    The NICE guidance for complex fractures and non-complex fractures supports structured orthopaedic appraisal, imaging, pain management and referral according to injury severity.

    Clinical orthopaedic illustration relevant to weight bearing after fracture
    Orthopaedic appraisal connects clinical concerns, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan should explain the likely diagnosis, alternatives, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    A fall, new deformity, sudden pain or damaged fixation requires prompt review.

    Frequently asked questions

    Can weight bearing after fracture be diagnosed from this symptom alone?

    No. Pain alone is not a precise weight-bearing prescription. A focused history and examination are needed before choosing patient-specific management.

    What should make me seek help sooner?

    A fall, new deformity, sudden pain or damaged fixation requires prompt review.

    How long should improvement take?

    There is no universal deadline. The diagnosis, severity, health, patient-specific management and functional demands affect progress; agree on a review point rather than waiting indefinitely.

    Do I need an MRI?

    Not automatically. Relevant imaging depends on the history, examination, previous results and whether the answer could change patient-specific management.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating movement, but complete rest is not always helpful. The safe level depends on the diagnosis and severity.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe for you, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    Does seeing an orthopaedic surgeon mean surgery?

    No. Orthopaedic orthopaedic appraisal includes diagnosis, non-surgical planning, monitoring and referral as well as surgery when appropriate.

    What should I bring to the appointment?

    Bring a medicine and allergy list, existing images and reports, relevant patient-specific management notes and a short timeline of clinical concerns or injury.

    Conclusion

    Weight-bearing instructions depend on fracture location, stability, fixation, healing stage, pain and balance. Terms such as non-weight-bearing, partial and weight-bearing as tolerated should be explained and demonstrated. The safest next step is a proportionate orthopaedic appraisal that connects the symptom or injury with your health, goals and the evidence. A useful plan should also say what would prompt earlier review.

    Medical references

    1. AAOS OrthoInfo — Open Fractures
    2. AAOS OrthoInfo — Internal Fixation for Fractures
    3. AAOS OrthoInfo — Cast Care
    4. NICE — Fractures (complex): orthopaedic appraisal and management
    5. NICE — Fractures (non-complex): orthopaedic appraisal and management

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical orthopaedic appraisal, diagnosis or patient-specific management. If clinical concerns are severe, urgent or worsening, seek appropriate medical care promptly.

  • When Is Fracture Surgery Discussed?

    When Is Fracture Surgery Discussed?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    Fracture surgery may be discussed when alignment, stability, joint involvement, open injury, soft-tissue damage or expected function cannot be managed adequately without fixation. The agreed recommendation depends on the exact fracture and patient.

    When Is Fracture Surgery Discussed — medically relevant orthopaedic illustration

    Short answer

    Fracture surgery may be discussed when alignment, stability, joint involvement, open injury, soft-tissue damage or expected function cannot be managed adequately without fixation. The agreed recommendation depends on the exact fracture and patient.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the careful clinical review and decision process before an individual consultation.

    Key takeaways

    Main pointFracture surgery may be discussed when alignment, stability, joint involvement, open injury, soft-tissue damage or expected function cannot be managed adequately without fixation. The agreed recommendation depends on the exact fracture and patient.
    Useful cluesAsk what problem fixation solves and what non-surgical option remains.
    Careful clinical reviewCareful clinical review reviews imaging, skin, circulation, nerves, health and functional demands.
    Possible pathwayBenefits are weighed against infection, anaesthesia, implant and healing risks.
    Important limitMetalwork does not make a fracture instantly healed or guarantee normal function.

    For the complete specialist pathway, reported symptom pattern assessed and appointment information, read about fracture surgery careful clinical review in Seremban.

    Treat the injury pattern, not only the X-ray

    Fracture surgery may be discussed when alignment, stability, joint involvement, open injury, soft-tissue damage or expected function cannot be managed adequately without fixation. The agreed recommendation depends on the exact fracture and patient. Ask what problem fixation solves and what non-surgical option remains.

    The force, skin condition, circulation, nerves and nearby joints can be as important as the break itself. Trauma careful clinical review first identifies threats to life and limb, then defines the fracture and soft-tissue injury.

    What the first examination checks

    Careful clinical review reviews imaging, skin, circulation, nerves, health and functional demands. Pain relief and temporary splinting may be needed before the full careful clinical review can be completed safely.

    The whole limb is examined because an obvious fracture can distract from another injury. Tell the team about numbness, tingling, colour change, wounds, medicines, allergies and the time of injury.

    How imaging helps define the fracture

    X-rays usually show location, pattern, displacement and joint involvement. CT or other imaging may be used for more complex questions or surgical planning, while repeat X-rays can show alignment and healing over time.

    Images remain one part of the decision. Skin, swelling, wound contamination, circulation, function, medical health and patient needs influence urgency and individualised care.

    How stability and alignment shape individualised care

    Benefits are weighed against infection, anaesthesia, implant and healing risks. The shared objective is a position and environment that gives the bone and soft tissues a reasonable chance to heal while preserving useful function.

    Some fractures are treated with a splint, cast or brace; others need reduction or fixation. The method can change as swelling settles or when follow-up shows that alignment has shifted.

    Healing is biological and mechanical

    Bone needs blood supply, stability and time. Smoking, infection, severe soft-tissue damage, nutrition, medicines and medical conditions can slow progress, while too much or too little loading may create different problems.

    Follow weight-bearing and device instructions exactly. Feeling less pain does not prove that the fracture has regained full strength, and persistent discomfort does not automatically mean that healing has failed.

    Rehabilitation protects function

    Joints and muscles lose movement, strength and confidence during protection. Rehabilitation may begin with safe movement of unaffected areas and progress as stability allows.

    The programme should reflect the bone involved, fixation, soft-tissue injury and tasks you need to regain. Forcing a generic timeline can overload healing tissue or leave important weakness unaddressed.

    Recognise limitations and uncertainty

    Metalwork does not make a fracture instantly healed or guarantee normal function. Ongoing follow-up exists because position, healing and reported symptom pattern can change.

    A careful explanation should include the main risks of both surgical and non-surgical care, the signs that agreed next step is working and the findings that would require a different approach.

    Use an explicit safety net

    The shared objective of this process is to connect the clinical findings with the movement, work, family responsibilities or activity that matters to you. A agreed next step should state what to do now, how long to try it and what would trigger review.

    Do not wait for a routine appointment when circulation, sensation, skin, wound or pain changes suggest urgent risk. The treating hospital or Emergency Department is the appropriate route for acute deterioration.

    Protect the whole limb during recovery

    A fracture affects more than the line seen on an X-ray. Swelling, skin, muscles, nearby joints, circulation, nerves and confidence can all change while the bone is protected. Follow instructions for elevation, movement of free joints, wound or pin care and use of walking aids, and ask before adding supplements or unplanned devices.

    At every review, compare the current limb with the previous week: pain trend, swelling, skin condition, finger or toe colour and sensation, device fit, movement and ability to manage daily tasks. A small deterioration can be important when it concerns circulation, infection, alignment or pressure inside a cast, even if the next routine appointment is close.

    How to use the consultation well

    Bring the questions that would change your decision, not only a request for a scan or procedure. Ask what diagnosis is most likely, what else is being considered, which finding supports agreed next step and what improvement would count as meaningful. For when fracture surgery is needed, it is also helpful to ask what you can safely continue while the careful clinical review or individualised care is in progress.

    Before leaving, confirm the review point and the safety net. Take time to know who will explain any test result, how long the agreed individualised care deserves, which activities should be modified and which new reported symptom pattern need earlier contact. Write agreed next step down or ask for it in a form you can understand; uncertainty is easier to manage when the next decision is explicit.

    What a responsible plan should contain

    A careful clinical review-led plan for when fracture surgery is needed should name the working diagnosis, acknowledge important uncertainty and connect each recommendation with a purpose. It should explain expected benefit, relevant harms, alternatives, practical demands and what may happen if individualised care is delayed or declined. When a test is suggested, ask which question it is meant to answer and how each possible result would change the next step.

    Agreed next step should also respect individual health, work, caregiving, financial and activity circumstances without turning those factors into guarantees. Confirm the review date, the measures of progress and the warning signs that override the routine timeline. Clear safety-netting protects patients from waiting too long when the pattern changes, while a defined follow-up prevents unnecessary escalation when recovery is proceeding appropriately.

    What clinical guidance supports

    The AAOS OrthoInfo — Open Fractures explains why a wound communicating with a fracture needs urgent infection control and stabilisation.

    AAOS OrthoInfo — Internal Fixation for Fractures describes plates, screws, nails and wires as methods for selected fractures, while AAOS OrthoInfo — Cast Care highlights cast protection and warning reported symptom pattern.

    The NICE guidance for complex fractures and non-complex fractures supports structured careful clinical review, imaging, pain management and referral according to injury severity.

    Clinical orthopaedic illustration relevant to when fracture surgery is needed
    Careful clinical review connects reported symptom pattern, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan should explain the likely diagnosis, alternatives, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    Open fractures and compromised circulation or nerves require emergency pathways.

    Frequently asked questions

    Can when fracture surgery is needed be diagnosed from this symptom alone?

    No. Metalwork does not make a fracture instantly healed or guarantee normal function. A focused history and examination are needed before choosing individualised care.

    What should make me seek help sooner?

    Open fractures and compromised circulation or nerves require emergency pathways.

    How long should improvement take?

    There is no universal deadline. The diagnosis, severity, health, individualised care and functional demands affect progress; agree on a review point rather than waiting indefinitely.

    Do I need an MRI?

    Not automatically. Imaging review depends on the history, examination, previous results and whether the answer could change individualised care.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating movement, but complete rest is not always helpful. The safe level depends on the diagnosis and severity.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe for you, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    Does seeing an orthopaedic surgeon mean surgery?

    No. Orthopaedic careful clinical review includes diagnosis, non-surgical planning, monitoring and referral as well as surgery when appropriate.

    What should I bring to the appointment?

    Bring a medicine and allergy list, existing images and reports, relevant individualised care notes and a short timeline of reported symptom pattern or injury.

    Conclusion

    Fracture surgery may be discussed when alignment, stability, joint involvement, open injury, soft-tissue damage or expected function cannot be managed adequately without fixation. The agreed recommendation depends on the exact fracture and patient. The safest next step is a proportionate careful clinical review that connects the symptom or injury with your health, goals and the evidence. A useful plan should also say what would prompt earlier review.

    Medical references

    1. AAOS OrthoInfo — Open Fractures
    2. AAOS OrthoInfo — Internal Fixation for Fractures
    3. AAOS OrthoInfo — Cast Care
    4. NICE — Fractures (complex): careful clinical review and management
    5. NICE — Fractures (non-complex): careful clinical review and management

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical careful clinical review, diagnosis or individualised care. If reported symptom pattern are severe, urgent or worsening, seek appropriate medical care promptly.

  • Delayed Fracture Healing: What Does It Mean?

    Delayed Fracture Healing: What Does It Mean?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    Delayed healing means a fracture is progressing more slowly than expected for its pattern and circumstances. It prompts review of stability, blood supply, infection, smoking, nutrition, health and adherence without assuming immediate surgery.

    Delayed Fracture Healing What Does It Mean — medically relevant orthopaedic illustration

    Short answer

    Delayed healing means a fracture is progressing more slowly than expected for its pattern and circumstances. It prompts review of stability, blood supply, infection, smoking, nutrition, health and adherence without assuming immediate surgery.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the orthopaedic review and decision process before an individual consultation.

    Key takeaways

    Main pointDelayed healing means a fracture is progressing more slowly than expected for its pattern and circumstances. It prompts review of stability, blood supply, infection, smoking, nutrition, health and adherence without assuming immediate surgery.
    Useful cluesReport persistent focal pain, motion, wound issues and any continued smoking or medical problems honestly.
    Orthopaedic reviewOrthopaedic review may use repeat imaging and targeted investigations.
    Possible pathwayManagement plan can include longer protection, risk-factor optimisation, stimulation techniques or surgery in selected cases.
    Important limitA slow X-ray appearance does not have one universal deadline or remedy.

    For the complete specialist pathway, clinical pattern assessed and appointment information, read about delayed fracture healing orthopaedic review in Seremban.

    Treat the injury pattern, not only the X-ray

    Delayed healing means a fracture is progressing more slowly than expected for its pattern and circumstances. It prompts review of stability, blood supply, infection, smoking, nutrition, health and adherence without assuming immediate surgery. Report persistent focal pain, motion, wound issues and any continued smoking or medical problems honestly.

    The force, skin condition, circulation, nerves and nearby joints can be as important as the break itself. Trauma orthopaedic review first identifies threats to life and limb, then defines the fracture and soft-tissue injury.

    What the first examination checks

    Orthopaedic review may use repeat imaging and targeted investigations. Pain relief and temporary splinting may be needed before the full orthopaedic review can be completed safely.

    The whole limb is examined because an obvious fracture can distract from another injury. Tell the team about numbness, tingling, colour change, wounds, medicines, allergies and the time of injury.

    How imaging helps define the fracture

    X-rays usually show location, pattern, displacement and joint involvement. CT or other imaging may be used for more complex questions or surgical planning, while repeat X-rays can show alignment and healing over time.

    Images remain one part of the decision. Skin, swelling, wound contamination, circulation, function, medical health and patient needs influence urgency and management plan.

    How stability and alignment shape management plan

    Management plan can include longer protection, risk-factor optimisation, stimulation techniques or surgery in selected cases. The treatment aim is a position and environment that gives the bone and soft tissues a reasonable chance to heal while preserving useful function.

    Some fractures are treated with a splint, cast or brace; others need reduction or fixation. The method can change as swelling settles or when follow-up shows that alignment has shifted.

    Healing is biological and mechanical

    Bone needs blood supply, stability and time. Smoking, infection, severe soft-tissue damage, nutrition, medicines and medical conditions can slow progress, while too much or too little loading may create different problems.

    Follow weight-bearing and device instructions exactly. Feeling less pain does not prove that the fracture has regained full strength, and persistent discomfort does not automatically mean that healing has failed.

    Rehabilitation protects function

    Joints and muscles lose movement, strength and confidence during protection. Rehabilitation may begin with safe movement of unaffected areas and progress as stability allows.

    The programme should reflect the bone involved, fixation, soft-tissue injury and tasks you need to regain. Forcing a generic timeline can overload healing tissue or leave important weakness unaddressed.

    Recognise limitations and uncertainty

    A slow X-ray appearance does not have one universal deadline or remedy. Progress review exists because position, healing and clinical pattern can change.

    A careful explanation should include the main risks of both surgical and non-surgical care, the signs that proposed pathway is working and the findings that would require a different approach.

    Use an explicit safety net

    The treatment aim of this process is to connect the clinical findings with the movement, work, family responsibilities or activity that matters to you. A proposed pathway should state what to do now, how long to try it and what would trigger review.

    Do not wait for a routine appointment when circulation, sensation, skin, wound or pain changes suggest urgent risk. The treating hospital or Emergency Department is the appropriate route for acute deterioration.

    Protect the whole limb during recovery

    A fracture affects more than the line seen on an X-ray. Swelling, skin, muscles, nearby joints, circulation, nerves and confidence can all change while the bone is protected. Follow instructions for elevation, movement of free joints, wound or pin care and use of walking aids, and ask before adding supplements or unplanned devices.

    At every review, compare the current limb with the previous week: pain trend, swelling, skin condition, finger or toe colour and sensation, device fit, movement and ability to manage daily tasks. A small deterioration can be important when it concerns circulation, infection, alignment or pressure inside a cast, even if the next routine appointment is close.

    How to use the consultation well

    Bring the questions that would change your decision, not only a request for a scan or procedure. Ask what diagnosis is most likely, what else is being considered, which finding supports proposed pathway and what improvement would count as meaningful. For delayed fracture healing, it is also helpful to ask what you can safely continue while the orthopaedic review or management plan is in progress.

    Before leaving, confirm the review point and the safety net. Try to know who will explain any test result, how long the agreed management plan deserves, which activities should be modified and which new clinical pattern need earlier contact. Write proposed pathway down or ask for it in a form you can understand; uncertainty is easier to manage when the next decision is explicit.

    What a responsible plan should contain

    A orthopaedic review-led plan for delayed fracture healing should name the working diagnosis, acknowledge important uncertainty and connect each recommendation with a purpose. It should explain expected benefit, relevant harms, alternatives, practical demands and what may happen if management plan is delayed or declined. When a test is suggested, ask which question it is meant to answer and how each possible result would change the next step.

    Proposed pathway should also respect individual health, work, caregiving, financial and activity circumstances without turning those factors into guarantees. Confirm the review date, the measures of progress and the warning signs that override the routine timeline. Clear safety-netting protects patients from waiting too long when the pattern changes, while a defined follow-up prevents unnecessary escalation when recovery is proceeding appropriately.

    What clinical guidance supports

    The AAOS OrthoInfo — Open Fractures explains why a wound communicating with a fracture needs urgent infection control and stabilisation.

    AAOS OrthoInfo — Internal Fixation for Fractures describes plates, screws, nails and wires as methods for selected fractures, while AAOS OrthoInfo — Cast Care highlights cast protection and warning clinical pattern.

    The NICE guidance for complex fractures and non-complex fractures supports structured orthopaedic review, imaging, pain management and referral according to injury severity.

    Clinical orthopaedic illustration relevant to delayed fracture healing
    Orthopaedic review connects clinical pattern, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan should explain the likely diagnosis, alternatives, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    Fever, drainage, increasing redness, deformity or sudden worsening requires earlier care.

    Frequently asked questions

    Can delayed fracture healing be diagnosed from this symptom alone?

    No. A slow X-ray appearance does not have one universal deadline or remedy. A focused history and examination are needed before choosing management plan.

    What should make me seek help sooner?

    Fever, drainage, increasing redness, deformity or sudden worsening requires earlier care.

    How long should improvement take?

    There is no universal deadline. The diagnosis, severity, health, management plan and functional demands affect progress; agree on a review point rather than waiting indefinitely.

    Do I need an MRI?

    Not automatically. Radiological tests depends on the history, examination, previous results and whether the answer could change management plan.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating movement, but complete rest is not always helpful. The safe level depends on the diagnosis and severity.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe for you, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    Does seeing an orthopaedic surgeon mean surgery?

    No. Orthopaedic orthopaedic review includes diagnosis, non-surgical planning, monitoring and referral as well as surgery when appropriate.

    What should I bring to the appointment?

    Bring a medicine and allergy list, existing images and reports, relevant management plan notes and a short timeline of clinical pattern or injury.

    Conclusion

    Delayed healing means a fracture is progressing more slowly than expected for its pattern and circumstances. It prompts review of stability, blood supply, infection, smoking, nutrition, health and adherence without assuming immediate surgery. The safest next step is a proportionate orthopaedic review that connects the symptom or injury with your health, goals and the evidence. A useful plan should also say what would prompt earlier review.

    Medical references

    1. AAOS OrthoInfo — Open Fractures
    2. AAOS OrthoInfo — Internal Fixation for Fractures
    3. AAOS OrthoInfo — Cast Care
    4. NICE — Fractures (complex): orthopaedic review and management
    5. NICE — Fractures (non-complex): orthopaedic review and management

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical orthopaedic review, diagnosis or management plan. If clinical pattern are severe, urgent or worsening, seek appropriate medical care promptly.

  • Cast Care: How to Protect Skin, Circulation and Healing

    Cast Care: How to Protect Skin, Circulation and Healing

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    A cast protects alignment while bone and soft tissues heal. Keep it dry unless specifically designed otherwise, do not insert objects, and monitor swelling, skin, circulation, sensation and cast integrity.

    Cast Care How to Protect Skin, Circulation and Healing — medically relevant orthopaedic illustration

    Short answer

    A cast protects alignment while bone and soft tissues heal. Keep it dry unless specifically designed otherwise, do not insert objects, and monitor swelling, skin, circulation, sensation and cast integrity.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the structured review and decision process before an individual consultation.

    Key takeaways

    Main pointA cast protects alignment while bone and soft tissues heal. Keep it dry unless specifically designed otherwise, do not insert objects, and monitor swelling, skin, circulation, sensation and cast integrity.
    Useful cluesCheck exposed fingers or toes for colour, warmth, movement and sensation.
    Structured reviewCast review may be needed as swelling changes or pressure points develop.
    Possible pathwayElevation and approved movement of free joints may help, but follow the treating team’s instructions.
    Important limitDo not trim, reshape or remove a cast yourself unless you were given a specific removable device plan.

    For the complete specialist pathway, reported concerns assessed and appointment information, read about fracture cast care guidance.

    Treat the injury pattern, not only the X-ray

    A cast protects alignment while bone and soft tissues heal. Keep it dry unless specifically designed otherwise, do not insert objects, and monitor swelling, skin, circulation, sensation and cast integrity. Check exposed fingers or toes for colour, warmth, movement and sensation.

    The force, skin condition, circulation, nerves and nearby joints can be as important as the break itself. Trauma structured review first identifies threats to life and limb, then defines the fracture and soft-tissue injury.

    What the first examination checks

    Cast review may be needed as swelling changes or pressure points develop. Pain relief and temporary splinting may be needed before the full structured review can be completed safely.

    The whole limb is examined because an obvious fracture can distract from another injury. Tell the team about numbness, tingling, colour change, wounds, medicines, allergies and the time of injury.

    How imaging helps define the fracture

    X-rays usually show location, pattern, displacement and joint involvement. CT or other imaging may be used for more complex questions or surgical planning, while repeat X-rays can show alignment and healing over time.

    Images remain one part of the decision. Skin, swelling, wound contamination, circulation, function, medical health and patient needs influence urgency and treatment approach.

    How stability and alignment shape treatment approach

    Elevation and approved movement of free joints may help, but follow the treating team’s instructions. The care objective is a position and environment that gives the bone and soft tissues a reasonable chance to heal while preserving useful function.

    Some fractures are treated with a splint, cast or brace; others need reduction or fixation. The method can change as swelling settles or when follow-up shows that alignment has shifted.

    Healing is biological and mechanical

    Bone needs blood supply, stability and time. Smoking, infection, severe soft-tissue damage, nutrition, medicines and medical conditions can slow progress, while too much or too little loading may create different problems.

    Follow weight-bearing and device instructions exactly. Feeling less pain does not prove that the fracture has regained full strength, and persistent discomfort does not automatically mean that healing has failed.

    Rehabilitation protects function

    Joints and muscles lose movement, strength and confidence during protection. Rehabilitation may begin with safe movement of unaffected areas and progress as stability allows.

    The programme should reflect the bone involved, fixation, soft-tissue injury and tasks you need to regain. Forcing a generic timeline can overload healing tissue or leave important weakness unaddressed.

    Recognise limitations and uncertainty

    Do not trim, reshape or remove a cast yourself unless you were given a specific removable device plan. A review visit exists because position, healing and reported concerns can change.

    A careful explanation should include the main risks of both surgical and non-surgical care, the signs that next-step strategy is working and the findings that would require a different approach.

    Use an explicit safety net

    The care objective of this process is to connect the clinical findings with the movement, work, family responsibilities or activity that matters to you. A next-step strategy should state what to do now, how long to try it and what would trigger review.

    Do not wait for a routine appointment when circulation, sensation, skin, wound or pain changes suggest urgent risk. The treating hospital or Emergency Department is the appropriate route for acute deterioration.

    Protect the whole limb during recovery

    A fracture affects more than the line seen on an X-ray. Swelling, skin, muscles, nearby joints, circulation, nerves and confidence can all change while the bone is protected. Follow instructions for elevation, movement of free joints, wound or pin care and use of walking aids, and ask before adding supplements or unplanned devices.

    At every review, compare the current limb with the previous week: pain trend, swelling, skin condition, finger or toe colour and sensation, device fit, movement and ability to manage daily tasks. A small deterioration can be important when it concerns circulation, infection, alignment or pressure inside a cast, even if the next routine appointment is close.

    How to use the consultation well

    Bring the questions that would change your decision, not only a request for a scan or procedure. Ask what diagnosis is most likely, what else is being considered, which finding supports next-step strategy and what improvement would count as meaningful. For cast care after fracture, it is also helpful to ask what you can safely continue while the structured review or treatment approach is in progress.

    Before leaving, confirm the review point and the safety net. You can reasonably know who will explain any test result, how long the agreed treatment approach deserves, which activities should be modified and which new reported concerns need earlier contact. Write next-step strategy down or ask for it in a form you can understand; uncertainty is easier to manage when the next decision is explicit.

    What a responsible plan should contain

    A structured review-led plan for cast care after fracture should name the working diagnosis, acknowledge important uncertainty and connect each recommendation with a purpose. It should explain expected benefit, relevant harms, alternatives, practical demands and what may happen if treatment approach is delayed or declined. When a test is suggested, ask which question it is meant to answer and how each possible result would change the next step.

    Next-step strategy should also respect individual health, work, caregiving, financial and activity circumstances without turning those factors into guarantees. Confirm the review date, the measures of progress and the warning signs that override the routine timeline. Clear safety-netting protects patients from waiting too long when the pattern changes, while a defined follow-up prevents unnecessary escalation when recovery is proceeding appropriately.

    What clinical guidance supports

    The AAOS OrthoInfo — Open Fractures explains why a wound communicating with a fracture needs urgent infection control and stabilisation.

    AAOS OrthoInfo — Internal Fixation for Fractures describes plates, screws, nails and wires as methods for selected fractures, while AAOS OrthoInfo — Cast Care highlights cast protection and warning reported concerns.

    The NICE guidance for complex fractures and non-complex fractures supports structured structured review, imaging, pain management and referral according to injury severity.

    Clinical orthopaedic illustration relevant to cast care after fracture
    Structured review connects reported concerns, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan should explain the likely diagnosis, alternatives, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    Urgent review is needed for severe increasing pain, numbness, burning, blue or pale digits, foul odour, drainage or a wet broken cast.

    Frequently asked questions

    Can cast care after fracture be diagnosed from this symptom alone?

    No. Do not trim, reshape or remove a cast yourself unless you were given a specific removable device plan. A focused history and examination are needed before choosing treatment approach.

    What should make me seek help sooner?

    Urgent review is needed for severe increasing pain, numbness, burning, blue or pale digits, foul odour, drainage or a wet broken cast.

    How long should improvement take?

    There is no universal deadline. The diagnosis, severity, health, treatment approach and functional demands affect progress; agree on a review point rather than waiting indefinitely.

    Do I need an MRI?

    Not automatically. Targeted imaging depends on the history, examination, previous results and whether the answer could change treatment approach.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating movement, but complete rest is not always helpful. The safe level depends on the diagnosis and severity.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe for you, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    Does seeing an orthopaedic surgeon mean surgery?

    No. Orthopaedic structured review includes diagnosis, non-surgical planning, monitoring and referral as well as surgery when appropriate.

    What should I bring to the appointment?

    Bring a medicine and allergy list, existing images and reports, relevant treatment approach notes and a short timeline of reported concerns or injury.

    Conclusion

    A cast protects alignment while bone and soft tissues heal. Keep it dry unless specifically designed otherwise, do not insert objects, and monitor swelling, skin, circulation, sensation and cast integrity. The safest next step is a proportionate structured review that connects the symptom or injury with your health, goals and the evidence. A useful plan should also say what would prompt earlier review.

    Medical references

    1. AAOS OrthoInfo — Open Fractures
    2. AAOS OrthoInfo — Internal Fixation for Fractures
    3. AAOS OrthoInfo — Cast Care
    4. NICE — Fractures (complex): structured review and management
    5. NICE — Fractures (non-complex): structured review and management

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical structured review, diagnosis or treatment approach. If reported concerns are severe, urgent or worsening, seek appropriate medical care promptly.

  • Why Do Fractures Heal at Different Speeds?

    Why Do Fractures Heal at Different Speeds?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    Fracture healing depends on bone involved, pattern, blood supply, soft-tissue damage, stability, age, health, smoking, nutrition and management approach. Timelines are estimates and should be judged with problems, examination and follow-up imaging.

    Why Do Fractures Heal at Different Speeds — medically relevant orthopaedic illustration

    Short answer

    Fracture healing depends on bone involved, pattern, blood supply, soft-tissue damage, stability, age, health, smoking, nutrition and management approach. Timelines are estimates and should be judged with problems, examination and follow-up imaging.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the focused review and decision process before an individual consultation.

    Key takeaways

    Main pointFracture healing depends on bone involved, pattern, blood supply, soft-tissue damage, stability, age, health, smoking, nutrition and management approach. Timelines are estimates and should be judged with problems, examination and follow-up imaging.
    Useful cluesAsk what signs of progress are expected at each review and which activities remain restricted.
    Focused reviewThe treating clinician assesses pain trend, function, tenderness, alignment and radiographic healing.
    Possible pathwayProtection and rehabilitation change as healing becomes secure enough for more load.
    Important limitFeeling better does not always mean the bone can tolerate unrestricted activity.

    For the complete specialist pathway, problems assessed and appointment information, read about fracture healing focused review in Seremban.

    Treat the injury pattern, not only the X-ray

    Fracture healing depends on bone involved, pattern, blood supply, soft-tissue damage, stability, age, health, smoking, nutrition and management approach. Timelines are estimates and should be judged with problems, examination and follow-up imaging. Ask what signs of progress are expected at each review and which activities remain restricted.

    The force, skin condition, circulation, nerves and nearby joints can be as important as the break itself. Trauma focused review first identifies threats to life and limb, then defines the fracture and soft-tissue injury.

    What the first examination checks

    The treating clinician assesses pain trend, function, tenderness, alignment and radiographic healing. Pain relief and temporary splinting may be needed before the full focused review can be completed safely.

    The whole limb is examined because an obvious fracture can distract from another injury. Tell the team about numbness, tingling, colour change, wounds, medicines, allergies and the time of injury.

    How imaging helps define the fracture

    X-rays usually show location, pattern, displacement and joint involvement. CT or other imaging may be used for more complex questions or surgical planning, while repeat X-rays can show alignment and healing over time.

    Images remain one part of the decision. Skin, swelling, wound contamination, circulation, function, medical health and patient needs influence urgency and management approach.

    How stability and alignment shape management approach

    Protection and rehabilitation change as healing becomes secure enough for more load. The central objective is a position and environment that gives the bone and soft tissues a reasonable chance to heal while preserving useful function.

    Some fractures are treated with a splint, cast or brace; others need reduction or fixation. The method can change as swelling settles or when follow-up shows that alignment has shifted.

    Healing is biological and mechanical

    Bone needs blood supply, stability and time. Smoking, infection, severe soft-tissue damage, nutrition, medicines and medical conditions can slow progress, while too much or too little loading may create different problems.

    Follow weight-bearing and device instructions exactly. Feeling less pain does not prove that the fracture has regained full strength, and persistent discomfort does not automatically mean that healing has failed.

    Rehabilitation protects function

    Joints and muscles lose movement, strength and confidence during protection. Rehabilitation may begin with safe movement of unaffected areas and progress as stability allows.

    The programme should reflect the bone involved, fixation, soft-tissue injury and tasks you need to regain. Forcing a generic timeline can overload healing tissue or leave important weakness unaddressed.

    Recognise limitations and uncertainty

    Feeling better does not always mean the bone can tolerate unrestricted activity. The next review exists because position, healing and problems can change.

    A careful explanation should include the main risks of both surgical and non-surgical care, the signs that agreed approach is working and the findings that would require a different approach.

    Use an explicit safety net

    The central objective of this process is to connect the clinical findings with the movement, work, family responsibilities or activity that matters to you. A agreed approach should state what to do now, how long to try it and what would trigger review.

    Do not wait for a routine appointment when circulation, sensation, skin, wound or pain changes suggest urgent risk. The treating hospital or Emergency Department is the appropriate route for acute deterioration.

    Protect the whole limb during recovery

    A fracture affects more than the line seen on an X-ray. Swelling, skin, muscles, nearby joints, circulation, nerves and confidence can all change while the bone is protected. Follow instructions for elevation, movement of free joints, wound or pin care and use of walking aids, and ask before adding supplements or unplanned devices.

    At every review, compare the current limb with the previous week: pain trend, swelling, skin condition, finger or toe colour and sensation, device fit, movement and ability to manage daily tasks. A small deterioration can be important when it concerns circulation, infection, alignment or pressure inside a cast, even if the next routine appointment is close.

    How to use the consultation well

    Bring the questions that would change your decision, not only a request for a scan or procedure. Ask what diagnosis is most likely, what else is being considered, which finding supports agreed approach and what improvement would count as meaningful. For fracture healing time factors, it is also helpful to ask what you can safely continue while the focused review or management approach is in progress.

    Before leaving, confirm the review point and the safety net. Make sure you know who will explain any test result, how long the agreed management approach deserves, which activities should be modified and which new problems need earlier contact. Write agreed approach down or ask for it in a form you can understand; uncertainty is easier to manage when the next decision is explicit.

    What a responsible plan should contain

    A focused review-led plan for fracture healing time factors should name the working diagnosis, acknowledge important uncertainty and connect each recommendation with a purpose. It should explain expected benefit, relevant harms, alternatives, practical demands and what may happen if management approach is delayed or declined. When a test is suggested, ask which question it is meant to answer and how each possible result would change the next step.

    Agreed approach should also respect individual health, work, caregiving, financial and activity circumstances without turning those factors into guarantees. Confirm the review date, the measures of progress and the warning signs that override the routine timeline. Clear safety-netting protects patients from waiting too long when the pattern changes, while a defined follow-up prevents unnecessary escalation when recovery is proceeding appropriately.

    What clinical guidance supports

    The AAOS OrthoInfo — Open Fractures explains why a wound communicating with a fracture needs urgent infection control and stabilisation.

    AAOS OrthoInfo — Internal Fixation for Fractures describes plates, screws, nails and wires as methods for selected fractures, while AAOS OrthoInfo — Cast Care highlights cast protection and warning problems.

    The NICE guidance for complex fractures and non-complex fractures supports structured focused review, imaging, pain management and referral according to injury severity.

    Clinical orthopaedic illustration relevant to fracture healing time factors
    Focused review connects problems, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan should explain the likely diagnosis, alternatives, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    Increasing pain, deformity, wound problems or neurovascular problems need earlier review.

    Frequently asked questions

    Can fracture healing time factors be diagnosed from this symptom alone?

    No. Feeling better does not always mean the bone can tolerate unrestricted activity. A focused history and examination are needed before choosing management approach.

    What should make me seek help sooner?

    Increasing pain, deformity, wound problems or neurovascular problems need earlier review.

    How long should improvement take?

    There is no universal deadline. The diagnosis, severity, health, management approach and functional demands affect progress; agree on a review point rather than waiting indefinitely.

    Do I need an MRI?

    Not automatically. Selected scans depends on the history, examination, previous results and whether the answer could change management approach.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating movement, but complete rest is not always helpful. The safe level depends on the diagnosis and severity.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe for you, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    Does seeing an orthopaedic surgeon mean surgery?

    No. Orthopaedic focused review includes diagnosis, non-surgical planning, monitoring and referral as well as surgery when appropriate.

    What should I bring to the appointment?

    Bring a medicine and allergy list, existing images and reports, relevant management approach notes and a short timeline of problems or injury.

    Conclusion

    Fracture healing depends on bone involved, pattern, blood supply, soft-tissue damage, stability, age, health, smoking, nutrition and management approach. Timelines are estimates and should be judged with problems, examination and follow-up imaging. The safest next step is a proportionate focused review that connects the symptom or injury with your health, goals and the evidence. A useful plan should also say what would prompt earlier review.

    Medical references

    1. AAOS OrthoInfo — Open Fractures
    2. AAOS OrthoInfo — Internal Fixation for Fractures
    3. AAOS OrthoInfo — Cast Care
    4. NICE — Fractures (complex): focused review and management
    5. NICE — Fractures (non-complex): focused review and management

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical focused review, diagnosis or management approach. If problems are severe, urgent or worsening, seek appropriate medical care promptly.

  • When a Bone Injury Needs Emergency Assessment

    When a Bone Injury Needs Emergency Assessment

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Patient guide

    Emergency clinical review is appropriate when a bone injury involves an open wound, major deformity, compromised circulation or sensation, severe pain, high-energy trauma or inability to use the limb. Protect the area and avoid repeated manipulation.

    When a Bone Injury Needs Emergency Assessment — medically relevant orthopaedic illustration

    Short answer

    Emergency clinical review is appropriate when a bone injury involves an open wound, major deformity, compromised circulation or sensation, severe pain, high-energy trauma or inability to use the limb. Protect the area and avoid repeated manipulation.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the clinical review and decision process before an individual consultation.

    Key takeaways

    Main pointEmergency clinical review is appropriate when a bone injury involves an open wound, major deformity, compromised circulation or sensation, severe pain, high-energy trauma or inability to use the limb. Protect the area and avoid repeated manipulation.
    Useful cluesCheck for bleeding, skin tension, colour, temperature, sensation and associated head, chest or abdominal injury.
    Clinical reviewTrauma care prioritises life-threatening problems before definitive fracture management.
    Possible pathwaySplinting, imaging, antibiotics for selected open injuries and surgical review may be required.
    Important limitDo not push a visible bone back or test an unstable limb repeatedly.

    For the complete specialist pathway, symptom pattern assessed and appointment information, read about urgent fracture and trauma care in Seremban.

    Treat the injury pattern, not only the X-ray

    Emergency clinical review is appropriate when a bone injury involves an open wound, major deformity, compromised circulation or sensation, severe pain, high-energy trauma or inability to use the limb. Protect the area and avoid repeated manipulation. Check for bleeding, skin tension, colour, temperature, sensation and associated head, chest or abdominal injury.

    The force, skin condition, circulation, nerves and nearby joints can be as important as the break itself. Trauma clinical review first identifies threats to life and limb, then defines the fracture and soft-tissue injury.

    What the first examination checks

    Trauma care prioritises life-threatening problems before definitive fracture management. Pain relief and temporary splinting may be needed before the full clinical review can be completed safely.

    The whole limb is examined because an obvious fracture can distract from another injury. Tell the team about numbness, tingling, colour change, wounds, medicines, allergies and the time of injury.

    How imaging helps define the fracture

    X-rays usually show location, pattern, displacement and joint involvement. CT or other imaging may be used for more complex questions or surgical planning, while repeat X-rays can show alignment and healing over time.

    Images remain one part of the decision. Skin, swelling, wound contamination, circulation, function, medical health and patient needs influence urgency and management.

    How stability and alignment shape management

    Splinting, imaging, antibiotics for selected open injuries and surgical review may be required. The practical objective is a position and environment that gives the bone and soft tissues a reasonable chance to heal while preserving useful function.

    Some fractures are treated with a splint, cast or brace; others need reduction or fixation. The method can change as swelling settles or when follow-up shows that alignment has shifted.

    Healing is biological and mechanical

    Bone needs blood supply, stability and time. Smoking, infection, severe soft-tissue damage, nutrition, medicines and medical conditions can slow progress, while too much or too little loading may create different problems.

    Follow weight-bearing and device instructions exactly. Feeling less pain does not prove that the fracture has regained full strength, and persistent discomfort does not automatically mean that healing has failed.

    Rehabilitation protects function

    Joints and muscles lose movement, strength and confidence during protection. Rehabilitation may begin with safe movement of unaffected areas and progress as stability allows.

    The programme should reflect the bone involved, fixation, soft-tissue injury and tasks you need to regain. Forcing a generic timeline can overload healing tissue or leave important weakness unaddressed.

    Recognise limitations and uncertainty

    Do not push a visible bone back or test an unstable limb repeatedly. Planned review exists because position, healing and symptom pattern can change.

    A careful explanation should include the main risks of both surgical and non-surgical care, the signs that next-step approach is working and the findings that would require a different approach.

    Use an explicit safety net

    The practical objective of this process is to connect the clinical findings with the movement, work, family responsibilities or activity that matters to you. A next-step approach should state what to do now, how long to try it and what would trigger review.

    Do not wait for a routine appointment when circulation, sensation, skin, wound or pain changes suggest urgent risk. The treating hospital or Emergency Department is the appropriate route for acute deterioration.

    Protect the whole limb during recovery

    A fracture affects more than the line seen on an X-ray. Swelling, skin, muscles, nearby joints, circulation, nerves and confidence can all change while the bone is protected. Follow instructions for elevation, movement of free joints, wound or pin care and use of walking aids, and ask before adding supplements or unplanned devices.

    At every review, compare the current limb with the previous week: pain trend, swelling, skin condition, finger or toe colour and sensation, device fit, movement and ability to manage daily tasks. A small deterioration can be important when it concerns circulation, infection, alignment or pressure inside a cast, even if the next routine appointment is close.

    How to use the consultation well

    Bring the questions that would change your decision, not only a request for a scan or procedure. Ask what diagnosis is most likely, what else is being considered, which finding supports next-step approach and what improvement would count as meaningful. For bone injury emergency, it is also helpful to ask what you can safely continue while the clinical review or management is in progress.

    Before leaving, confirm the review point and the safety net. You need to know who will explain any test result, how long the agreed management deserves, which activities should be modified and which new symptom pattern need earlier contact. Write next-step approach down or ask for it in a form you can understand; uncertainty is easier to manage when the next decision is explicit.

    What a responsible plan should contain

    A clinical review-led plan for bone injury emergency should name the working diagnosis, acknowledge important uncertainty and connect each recommendation with a purpose. It should explain expected benefit, relevant harms, alternatives, practical demands and what may happen if management is delayed or declined. When a test is suggested, ask which question it is meant to answer and how each possible result would change the next step.

    Next-step approach should also respect individual health, work, caregiving, financial and activity circumstances without turning those factors into guarantees. Confirm the review date, the measures of progress and the warning signs that override the routine timeline. Clear safety-netting protects patients from waiting too long when the pattern changes, while a defined follow-up prevents unnecessary escalation when recovery is proceeding appropriately.

    What clinical guidance supports

    The AAOS OrthoInfo — Open Fractures explains why a wound communicating with a fracture needs urgent infection control and stabilisation.

    AAOS OrthoInfo — Internal Fixation for Fractures describes plates, screws, nails and wires as methods for selected fractures, while AAOS OrthoInfo — Cast Care highlights cast protection and warning symptom pattern.

    The NICE guidance for complex fractures and non-complex fractures supports structured clinical review, imaging, pain management and referral according to injury severity.

    Clinical orthopaedic illustration relevant to bone injury emergency
    Clinical review connects symptom pattern, examination and appropriate imaging rather than relying on one sign alone.
    Dr Shaharil and orthopaedic clinical team in Seremban
    A clear plan should explain the likely diagnosis, alternatives, limitations, follow-up and urgent warning signs.

    When to seek urgent care

    Call emergency services when transport or the overall injury makes self-travel unsafe.

    Frequently asked questions

    Can bone injury emergency be diagnosed from this symptom alone?

    No. Do not push a visible bone back or test an unstable limb repeatedly. A focused history and examination are needed before choosing management.

    What should make me seek help sooner?

    Call emergency services when transport or the overall injury makes self-travel unsafe.

    How long should improvement take?

    There is no universal deadline. The diagnosis, severity, health, management and functional demands affect progress; agree on a review point rather than waiting indefinitely.

    Do I need an MRI?

    Not automatically. Appropriate imaging depends on the history, examination, previous results and whether the answer could change management.

    Should I stop all activity?

    Avoid unsafe or sharply aggravating movement, but complete rest is not always helpful. The safe level depends on the diagnosis and severity.

    Can I take pain medicine?

    Ask a doctor or pharmacist what is safe for you, especially with kidney, stomach, liver or heart conditions, pregnancy, blood thinners or other medicines.

    Does seeing an orthopaedic surgeon mean surgery?

    No. Orthopaedic clinical review includes diagnosis, non-surgical planning, monitoring and referral as well as surgery when appropriate.

    What should I bring to the appointment?

    Bring a medicine and allergy list, existing images and reports, relevant management notes and a short timeline of symptom pattern or injury.

    Conclusion

    Emergency clinical review is appropriate when a bone injury involves an open wound, major deformity, compromised circulation or sensation, severe pain, high-energy trauma or inability to use the limb. Protect the area and avoid repeated manipulation. The safest next step is a proportionate clinical review that connects the symptom or injury with your health, goals and the evidence. A useful plan should also say what would prompt earlier review.

    Medical references

    1. AAOS OrthoInfo — Open Fractures
    2. AAOS OrthoInfo — Internal Fixation for Fractures
    3. AAOS OrthoInfo — Cast Care
    4. NICE — Fractures (complex): clinical review and management
    5. NICE — Fractures (non-complex): clinical review and management

    Let’s work out what comes next.

    Tell the clinic what happened, what hurts and which movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical clinical review, diagnosis or management. If symptom pattern are severe, urgent or worsening, seek appropriate medical care promptly.