Category: Orthopaedic Guidance

  • Does Seeing an Orthopaedic Surgeon Always Mean Surgery?

    Does Seeing an Orthopaedic Surgeon Always Mean Surgery?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Assessment first, treatment second

    The word surgeon can make an appointment sound like a decision has already been made. It has not. Orthopaedic surgeons assess musculoskeletal conditions and use both non-surgical and surgical treatment pathways.
    Orthopaedic consultation illustration representing treatment choices

    Short answer

    No. An orthopaedic surgeon may recommend advice, rehabilitation, activity modification, medication, bracing, monitoring or another non-surgical option. Surgery is considered when the diagnosis, severity, likely benefits, limitations and your goals make it an appropriate choice.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the assessment and treatment pathway before an individual consultation.

    Key takeaways

    No commitmentAn orthopaedic consultation is an assessment, not consent for surgery.
    OptionsEducation, rehabilitation, activity change, medicines or injections may be considered where suitable.
    SurgeryDiscussed when the diagnosis, symptom burden and expected benefit justify it.
    Your choiceReasonable alternatives, risks, limitations and the option to wait should be explained.

    Orthopaedic care begins with diagnosis

    Bones, joints, ligaments, tendons and muscles can produce similar symptoms for different reasons. Before discussing treatment, the clinician needs to understand the history, examine the affected area and decide whether any investigation is necessary.

    Sometimes the most valuable outcome of the consultation is a clearer diagnosis and a structured non-surgical plan. In other situations, the assessment may show that monitoring, referral to another service or urgent care is more suitable.

    Non-surgical options are part of orthopaedics

    Depending on the condition, non-surgical care may include education, changes to activity, rehabilitation, medication, a brace or cast, weight-management support, injections when clinically appropriate, or follow-up over time. Not every option suits every person.

    The plan should address what you need to do in daily life and what outcome is realistic. A scan finding alone should not force a treatment decision without considering symptoms, function and personal priorities.

    When surgery enters the conversation

    Surgery may be discussed for a significant injury, progressive damage, instability, deformity, symptoms that remain limiting despite appropriate non-surgical care, or another problem where an operation offers a reasonable balance of benefit and risk.

    A recommendation is not the same as pressure. You should understand the purpose of the operation, alternatives, expected recovery, important risks, likely limitations and what may happen if you choose not to proceed at that time.

    The decision should be shared

    Shared decision making combines clinical evidence and professional judgement with your preferences and circumstances. The best option may differ between two people with similar imaging because their symptoms, health, work, support and goals are different.

    Ask for explanations in plain language. It is reasonable to take time, discuss the decision with family, return with more questions or seek another opinion when the situation is not urgent.

    What clinical guidance supports

    The AAOS description of orthopaedic practice includes diagnosis, prevention, rehabilitation and both non-surgical and surgical treatment. Seeing a surgeon therefore does not mean an operation has been chosen.

    The GMC consent principles require meaningful dialogue about benefits, harms, reasonable alternatives and the option to take no action. NICE osteoarthritis guidance likewise places exercise, information and appropriate weight management at the core of care before joint-replacement referral is considered for substantially affected quality of life.

    Dr Shaharil, Consultant Orthopaedic and Trauma Surgeon in Seremban
    A consultation should connect the clinical findings with the movement and daily activities that matter to you.

    What non-surgical care can involve

    A non-surgical plan may combine diagnosis-specific education, activity modification, progressive exercise or physiotherapy, occupational changes, a brace or walking aid, and medication review. Injections may be appropriate for selected conditions but are not a universal solution.

    The plan should state what improvement is realistic, how long to try it and what would count as failure. Non-surgical treatment is active treatment—not dismissal—and it needs the same follow-up discipline as a procedure.

    When surgery enters the discussion

    Surgery is more likely to be discussed when there is a structural problem that can be treated surgically, symptoms materially affect quality of life or safety, and reasonable alternatives are ineffective, unsuitable or unlikely to solve the problem. Urgent injuries are a different pathway from long-standing degenerative pain.

    A surgeon should explain the purpose of the procedure, important risks, expected recovery, rehabilitation demands and the chance that some symptoms may remain. No operation can guarantee a perfect result.

    It is reasonable to pause and ask questions

    Unless treatment is urgent, you can take time to consider the information, involve family and seek clarification. Ask what happens if you wait, which symptoms might progress, and whether a second opinion would be useful.

    Your decision should reflect your health, responsibilities, risk tolerance and goals. A technically possible operation is not automatically the best option for every person.

    How I turn uncertainty into a staged plan

    I usually organise the next step around three questions: what is safe to do now, what missing information would genuinely change treatment, and what development would make us revise the plan. The first step may be activity adjustment, diagnosis-specific rehabilitation, symptom relief or a targeted test. It should be proportionate to both the level of risk and the amount of function you have lost.

    Every plan also needs a review point. We should agree on the change we hope to see, a reasonable timescale and the findings that would mean the strategy is not enough. This avoids waiting indefinitely without direction and also avoids escalating to an invasive treatment before the diagnosis, alternatives and goals are clear.

    Personal factors that can change the recommendation

    Two people with similar scan findings may reasonably choose different plans. Work demands, caregiving, previous injuries, other health conditions, medicines, sport, sleep, willingness to complete rehabilitation and the movement you need to regain can all change the balance of benefit and burden.

    Tell the clinician about diabetes, heart, kidney or stomach problems, blood-thinning medicine, allergies, infection history, pregnancy where relevant, and previous operations or implants. These details do not automatically rule treatment in or out, but they can change medication safety, test selection, procedural risk, preparation and recovery planning.

    Orthopaedic discussion with Dr Shaharil at CMH Specialist Hospital
    A plan is clearer when benefits, limitations, alternatives and follow-up are discussed together.

    Questions worth asking

    • What are the realistic non-surgical options for my condition?
    • What problem would surgery be intended to solve?
    • What are the benefits, limitations and important risks?
    • What could happen if I wait or continue non-surgical treatment?
    • What recovery support would I need?

    When to seek urgent care

    Shared decision making applies to planned care, not emergencies. Major trauma, an open wound over a possible fracture, threatened circulation or sensation, or a hot swollen joint with fever requires urgent assessment.

    Frequently asked questions

    Can an orthopaedic surgeon prescribe physiotherapy?

    Rehabilitation may form part of a non-surgical or post-treatment plan when appropriate. The exact referral pathway depends on the condition and local service arrangements.

    Can I decide not to have an operation?

    For planned treatment, you should receive enough information to make an informed decision. Ask about alternatives and the likely consequences of waiting or declining.

    Is a second opinion acceptable before surgery?

    Yes, especially when the decision is significant or you remain uncertain. Bring the relevant images, reports and treatment history.

    Can an orthopaedic condition be diagnosed from symptoms alone?

    Symptoms are important, but similar symptoms can arise from different structures or conditions. A diagnosis may require a focused examination and, only when it will change management, an appropriate investigation.

    Should I stop all activity until I am assessed?

    Not automatically. Avoid movements that cause sharp pain, repeated giving way or clear worsening, but complete rest can sometimes increase stiffness and weakness. The safe level of activity depends on the cause and severity.

    Can I take pain medicine before the appointment?

    Do not start, stop or change medication solely because of this article. Ask a doctor or pharmacist what is safe for you, especially if you have kidney, stomach, liver or heart problems, take blood thinners, are pregnant, or use other medicines.

    What if my scan looks normal but I still have pain?

    A scan is one part of assessment. Some painful problems are diagnosed mainly from the history and examination, and some scan findings do not explain the symptoms. Persistent functional difficulty still deserves a clinical review.

    What should I monitor before follow-up?

    Note pain triggers, swelling, sleep disturbance, walking tolerance, work or sport limitations, episodes of locking or giving way, and whether the agreed plan is helping. This gives the follow-up visit useful information.

    Conclusion

    My role is not to steer every patient towards surgery. It is to identify the problem, explain the realistic options and help you choose a safe plan that fits both the evidence and your life.

    Medical references

    1. American Academy of Orthopaedic Surgeons — About Orthopaedists
    2. AAOS OrthoInfo — Your Visit With an Orthopaedic Surgeon
    3. NICE — Shared Decision Making
    4. NICE — Osteoarthritis in over 16s: diagnosis and management
    5. General Medical Council — The seven principles of decision making and consent

    About Dr Shaharil

    Dr Shaharil is a Consultant Orthopaedic & Trauma Surgeon practising at CMH Specialist Hospital in Seremban. Learn more about Dr Shaharil.

    Let’s begin with a clear conversation.

    Tell the clinic what hurts, when it began and what movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical assessment, diagnosis or treatment. If symptoms are severe or worsening, seek appropriate medical care promptly.
  • Do I Need an X-ray or MRI for Joint Pain?

    Do I Need an X-ray or MRI for Joint Pain?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Choose the test that answers the right question

    A scan can be valuable, but only when it is matched to a useful clinical question. The best starting point is often your symptoms and examination—not choosing an MRI before anyone has assessed the problem.

    Clinical assessment illustration representing decisions about joint imaging

    Short answer

    Not every episode of joint pain requires imaging. X-rays are often useful for bones, alignment, fractures and joint-space changes, while MRI can show soft tissues and structures that are not seen well on a standard X-ray. The appropriate test depends on the suspected condition, examination and previous results.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the assessment and treatment pathway before an individual consultation.

    Key takeaways

    X-rayBest suited to many bone, alignment, fracture and arthritis questions.
    MRIShows soft tissues and bone marrow detail but is not automatically the first test.
    SequenceHistory and examination define the question before the scan is selected.
    MeaningImaging findings must be matched with symptoms; an abnormality may be incidental.

    The clinical question comes first

    Imaging is most useful when the result could clarify a diagnosis, rule out an important problem or change the treatment plan. The same test is not appropriate for every painful knee, shoulder, hip or limb.

    Your clinician will consider how the symptoms started, whether there was trauma, the pattern of pain, swelling or instability and what the examination shows. This helps decide whether imaging is needed now, later or not at all.

    What an X-ray may show

    X-rays are particularly useful for bone and joint alignment. They may show a fracture, dislocation, changes associated with arthritis or other bony abnormalities. Weight-bearing views can sometimes provide information that a non-weight-bearing image does not.

    An X-ray does not show every structure clearly. A normal X-ray does not automatically mean that nothing is wrong, just as an abnormal-looking X-ray does not by itself explain exactly how much pain someone feels.

    When MRI may add information

    MRI can provide detailed images of soft tissues such as menisci, ligaments, tendons, cartilage and bone marrow. It may be considered when the history, examination and initial imaging suggest a question that MRI can answer.

    MRI can also show findings that are common in people without symptoms. That is why the scan must be interpreted in the context of where you hurt, how the problem behaves and what the examination reveals. Treating an image rather than the person can lead to confusion.

    Bring previous images whenever possible

    Previous scans allow comparison and may reduce unnecessary repetition. Bring the report and, if possible, the actual images in a format the hospital can access. Note when the scan was performed and whether your symptoms have changed since then.

    If another scan is recommended, ask what the clinician is looking for, how the result may influence the plan and whether there are alternatives. These are reasonable shared-decision questions.

    What clinical guidance supports

    The ACR/RSNA patient resource on musculoskeletal MRI notes that bones and joints are commonly assessed first with X-rays, while MRI can provide detailed soft-tissue information without ionising radiation.

    Imaging choice changes with the situation. The ACR acute-knee-trauma criteria favour radiographs first when trauma is accompanied by focal tenderness, swelling in the joint or inability to bear weight; MRI may follow when an occult fracture or internal injury remains suspected after radiographs. For typical osteoarthritis, NICE advises against routine imaging for diagnosis or follow-up unless atypical features suggest another problem.

    Clinical anatomical illustration of the shoulder joint
    Imaging is most useful when it answers a specific question raised by the history and examination.

    What each test is designed to answer

    X-rays are strong for fractures, joint-space narrowing, bone shape, alignment and some signs of arthritis. They are quick and often weight-bearing views provide functional information. They do not show every tendon, ligament, cartilage or early stress injury.

    MRI can show ligaments, tendons, cartilage, menisci, muscles, bone marrow and other soft tissues in greater detail. That detail is valuable when it changes management, but it can also reveal age-related or incidental findings unrelated to the pain.

    Why ‘more detailed’ does not always mean ‘better first’

    A test is useful when there is a precise clinical question and the result can change a decision. Ordering an MRI before understanding the symptom pattern may create anxiety, cost and delay without improving treatment. In some cases, no immediate imaging is the evidence-based choice.

    Conversely, imaging should not be withheld when the history or examination raises concern for fracture, infection, tumour, significant trauma, progressive neurological change or a problem that requires procedural planning. The sequence should be proportionate to risk.

    Questions to ask before any scan

    Ask what diagnosis the scan is testing, whether a simpler test should come first, how the result would change treatment and what happens if the scan is normal. Tell the team about pregnancy, metal implants, pacemakers, kidney disease, severe claustrophobia or previous contrast reactions when relevant.

    Bring old images for comparison. A new scan is not automatically more useful than reviewing an existing study alongside a current examination.

    How I turn uncertainty into a staged plan

    I usually organise the next step around three questions: what is safe to do now, what missing information would genuinely change treatment, and what development would make us revise the plan. The first step may be activity adjustment, diagnosis-specific rehabilitation, symptom relief or a targeted test. It should be proportionate to both the level of risk and the amount of function you have lost.

    Every plan also needs a review point. We should agree on the change we hope to see, a reasonable timescale and the findings that would mean the strategy is not enough. This avoids waiting indefinitely without direction and also avoids escalating to an invasive treatment before the diagnosis, alternatives and goals are clear.

    Personal factors that can change the recommendation

    Two people with similar scan findings may reasonably choose different plans. Work demands, caregiving, previous injuries, other health conditions, medicines, sport, sleep, willingness to complete rehabilitation and the movement you need to regain can all change the balance of benefit and burden.

    Tell the clinician about diabetes, heart, kidney or stomach problems, blood-thinning medicine, allergies, infection history, pregnancy where relevant, and previous operations or implants. These details do not automatically rule treatment in or out, but they can change medication safety, test selection, procedural risk, preparation and recovery planning.

    Orthopaedic discussion with Dr Shaharil at CMH Specialist Hospital
    A plan is clearer when benefits, limitations, alternatives and follow-up are discussed together.

    Questions to ask before imaging

    • What clinical question is this test intended to answer?
    • Could the result change my treatment or activity advice?
    • Do my previous images already provide useful information?
    • Are there limitations or incidental findings I should understand?

    When to seek urgent care

    Imaging decisions are different in emergencies. Seek urgent assessment after major trauma, with deformity, inability to bear weight, severe swelling, loss of feeling, a cold or pale limb, or fever with a hot and red joint.

    Frequently asked questions

    Is MRI always better than X-ray?

    No. They answer different questions. X-rays are often the appropriate first test for bone, alignment and arthritis, while MRI may add soft-tissue detail when clinically indicated.

    Can a scan diagnose the cause of pain by itself?

    Usually it needs context. Imaging findings should be matched with your symptoms, examination and medical history.

    Should I repeat an old scan?

    Not automatically. Bring the existing study and explain how your symptoms have changed. The clinician can decide whether updated imaging would add value.

    Can the cause of joint pain be diagnosed from symptoms alone?

    Symptoms are important, but similar symptoms can arise from different structures or conditions. A diagnosis may require a focused examination and, only when it will change management, an appropriate investigation.

    Should I stop all activity until I am assessed?

    Not automatically. Avoid movements that cause sharp pain, repeated giving way or clear worsening, but complete rest can sometimes increase stiffness and weakness. The safe level of activity depends on the cause and severity.

    Can I take pain medicine before the appointment?

    Do not start, stop or change medication solely because of this article. Ask a doctor or pharmacist what is safe for you, especially if you have kidney, stomach, liver or heart problems, take blood thinners, are pregnant, or use other medicines.

    What if my scan looks normal but I still have pain?

    A scan is one part of assessment. Some painful problems are diagnosed mainly from the history and examination, and some scan findings do not explain the symptoms. Persistent functional difficulty still deserves a clinical review.

    What should I monitor before follow-up?

    Note pain triggers, swelling, sleep disturbance, walking tolerance, work or sport limitations, episodes of locking or giving way, and whether the agreed plan is helping. This gives the follow-up visit useful information.

    Conclusion

    The most useful scan is not necessarily the most advanced one. It is the test—if any—that answers the right question at the right time and changes what we do next.

    Medical references

    1. RadiologyInfo.org (ACR/RSNA) — Musculoskeletal MRI
    2. American College of Radiology — Appropriateness Criteria for Chronic Knee Pain
    3. American College of Radiology — Acute Trauma to the Knee
    4. NICE — Osteoarthritis in over 16s: diagnosis and management
    5. AAOS OrthoInfo — Your Visit With an Orthopaedic Surgeon

    About Dr Shaharil

    Dr Shaharil is a Consultant Orthopaedic & Trauma Surgeon practising at CMH Specialist Hospital in Seremban. Learn more about Dr Shaharil.

    Let’s begin with a clear conversation.

    Tell the clinic what hurts, when it began and what movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical assessment, diagnosis or treatment. If symptoms are severe or worsening, seek appropriate medical care promptly.

  • When Does Bone or Joint Pain Need Specialist Assessment?

    When Does Bone or Joint Pain Need Specialist Assessment?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Know when a closer look may help

    Many aches improve with time, sensible activity changes and appropriate first-line care. Specialist assessment becomes more useful when symptoms persist, recur, follow an injury or begin limiting the life you want to lead.

    Orthopaedic assessment illustration for bone and joint pain

    Short answer

    Consider an orthopaedic assessment when bone or joint pain is not improving as expected, repeatedly returns, affects sleep or daily function, or is accompanied by swelling, stiffness, weakness, instability or loss of movement. Significant injuries and urgent warning signs need earlier care.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the assessment and treatment pathway before an individual consultation.

    Key takeaways

    TimePain that persists, recurs or progressively limits function deserves assessment.
    FunctionWalking, sleep, work, self-care and joint stability matter as much as a pain score.
    UrgencyDeformity, inability to bear weight, a hot swollen joint with fever, or new numbness needs urgent care.
    Specialist roleAssessment does not commit you to surgery; it clarifies the diagnosis and treatment pathway.

    The effect on function matters

    Pain intensity is only one part of the story. Difficulty walking, climbing stairs, lifting, working, sleeping, exercising or caring for yourself may justify a closer assessment even if you can still manage some activities.

    Notice whether the problem is gradually improving, staying the same or getting worse. Repeated flare-ups can also be important, especially when they make a joint feel unreliable or force you to keep changing your routine.

    Some symptom patterns deserve specialist review

    Persistent swelling, stiffness, restricted movement, weakness, locking, catching or giving way can point to different musculoskeletal problems. These symptoms cannot be diagnosed accurately from a checklist alone, but they provide useful reasons to examine the joint or limb properly.

    An assessment may also help if you already have a diagnosis or scan but do not understand what it means, your recovery has stalled, or you want to discuss the available treatment pathways more clearly.

    Injuries change the timing

    Pain after a fall, collision, twist or direct impact should be judged according to the force of injury and your current function. Inability to bear weight, significant swelling, visible deformity or loss of normal movement should not be treated like a routine ache.

    A suspected fracture, unstable joint or injury that is not recovering as expected may need examination and appropriate imaging. When symptoms are severe or circulation and sensation appear affected, emergency care is more appropriate than an ordinary clinic appointment.

    An assessment does not commit you to surgery

    Orthopaedic specialists diagnose and manage musculoskeletal conditions using both non-surgical and surgical approaches. The next step may be advice, rehabilitation, medication review, bracing, further investigation, monitoring or a procedure, depending on the diagnosis and your needs.

    The purpose of the appointment is to understand the problem and discuss appropriate options. You should be able to ask about benefits, limitations, alternatives and what may happen if you choose to wait.

    What clinical guidance supports

    The NHS joint-pain guidance advises clinical review when pain affects normal activity or sleep, worsens, recurs or does not improve with initial self-care. It also identifies a hot swollen joint with systemic illness and inability to bear weight after injury as urgent patterns.

    For common osteoarthritis patterns, NICE guidance focuses management on symptoms and physical function and does not recommend routine imaging when the clinical picture is typical.

    Clinical anatomical illustration of the shoulder joint
    Imaging is most useful when it answers a specific question raised by the history and examination.

    Patterns that justify a closer look

    Specialist assessment becomes more useful when symptoms are persistent, progressively worsening, recurrent after reasonable treatment or difficult to explain. Repeated swelling, loss of movement, night pain, weakness, instability, a new lump or pain after a significant injury deserve context-specific review.

    The threshold is also lower when the problem threatens work safety, caregiving, independent walking or an important activity. You do not need to wait until pain is unbearable; a meaningful loss of function is a valid reason to seek help.

    Not every joint symptom belongs only to orthopaedics

    Joint pain can be mechanical, inflammatory, infective, neurological or referred from another area. Morning stiffness lasting a long time, several swollen joints, rash, fever or systemic illness may require coordination with primary care, rheumatology or another specialty.

    A careful clinician should be willing to redirect the pathway when the pattern points outside orthopaedic surgery. The goal is the correct care, not forcing every symptom into one specialty.

    What a proportionate plan may include

    Depending on the findings, the next step may be education, activity modification, rehabilitation, medication review, an X-ray or another targeted test. A specialist may also advise monitoring if the condition appears safe and self-limiting.

    Surgery is considered only for selected diagnoses and circumstances, usually after the likely benefits, limitations, recovery demands and non-surgical alternatives have been discussed. The severity of a scan alone should not replace the patient’s symptoms and goals.

    How I turn uncertainty into a staged plan

    I usually organise the next step around three questions: what is safe to do now, what missing information would genuinely change treatment, and what development would make us revise the plan. The first step may be activity adjustment, diagnosis-specific rehabilitation, symptom relief or a targeted test. It should be proportionate to both the level of risk and the amount of function you have lost.

    Every plan also needs a review point. We should agree on the change we hope to see, a reasonable timescale and the findings that would mean the strategy is not enough. This avoids waiting indefinitely without direction and also avoids escalating to an invasive treatment before the diagnosis, alternatives and goals are clear.

    Personal factors that can change the recommendation

    Two people with similar scan findings may reasonably choose different plans. Work demands, caregiving, previous injuries, other health conditions, medicines, sport, sleep, willingness to complete rehabilitation and the movement you need to regain can all change the balance of benefit and burden.

    Tell the clinician about diabetes, heart, kidney or stomach problems, blood-thinning medicine, allergies, infection history, pregnancy where relevant, and previous operations or implants. These details do not automatically rule treatment in or out, but they can change medication safety, test selection, procedural risk, preparation and recovery planning.

    Dr Shaharil, Consultant Orthopaedic and Trauma Surgeon in Seremban
    A consultation should connect the clinical findings with the movement and daily activities that matter to you.

    Consider booking an assessment when

    • Symptoms persist or keep returning despite reasonable initial care.
    • Pain or stiffness limits walking, work, sleep, exercise or daily activities.
    • A joint locks, catches, gives way or loses movement.
    • You have a fracture, significant injury or recovery that is not progressing as expected.
    • You have scans or a diagnosis but still need a clearer explanation of the options.

    When to seek urgent care

    Seek urgent help for major trauma, visible deformity, an open wound over a suspected fracture, severe uncontrolled pain, inability to use the limb, new numbness, or a limb that becomes cold or pale. Fever with a hot, red and swollen joint also needs urgent assessment.

    Frequently asked questions

    Should every joint ache see a specialist?

    No. Many minor aches improve with appropriate first-line care. Assessment becomes more useful when symptoms persist, recur, worsen or interfere with function.

    Can a specialist help if I already have a scan?

    Yes. A specialist can consider the images and report alongside your symptoms and examination, then explain what the findings may mean for treatment.

    What if I am unsure which joint or tissue is causing the pain?

    You do not need to diagnose yourself. Describe where you feel the problem, when it occurs and what movement has changed.

    Can bone or joint pain be diagnosed from symptoms alone?

    Symptoms are important, but similar symptoms can arise from different structures or conditions. A diagnosis may require a focused examination and, only when it will change management, an appropriate investigation.

    Should I stop all activity until I am assessed?

    Not automatically. Avoid movements that cause sharp pain, repeated giving way or clear worsening, but complete rest can sometimes increase stiffness and weakness. The safe level of activity depends on the cause and severity.

    Can I take pain medicine before the appointment?

    Do not start, stop or change medication solely because of this article. Ask a doctor or pharmacist what is safe for you, especially if you have kidney, stomach, liver or heart problems, take blood thinners, are pregnant, or use other medicines.

    What if my scan looks normal but I still have pain?

    A scan is one part of assessment. Some painful problems are diagnosed mainly from the history and examination, and some scan findings do not explain the symptoms. Persistent functional difficulty still deserves a clinical review.

    What should I monitor before follow-up?

    Note pain triggers, swelling, sleep disturbance, walking tolerance, work or sport limitations, episodes of locking or giving way, and whether the agreed plan is helping. This gives the follow-up visit useful information.

    Conclusion

    The best time to seek an orthopaedic opinion is not defined by one pain score. It is when the pattern, duration, loss of function, instability or uncertainty makes a structured assessment more useful than continuing to wait without a plan.

    Medical references

    1. American Academy of Orthopaedic Surgeons — About Orthopaedists
    2. AAOS OrthoInfo — Your Visit With an Orthopaedic Surgeon
    3. NHS — Joint pain
    4. NICE — Osteoarthritis in over 16s: diagnosis and management
    5. NICE — Shared Decision Making

    About Dr Shaharil

    Dr Shaharil is a Consultant Orthopaedic & Trauma Surgeon practising at CMH Specialist Hospital in Seremban. Learn more about Dr Shaharil.

    Let’s begin with a clear conversation.

    Tell the clinic what hurts, when it began and what movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical assessment, diagnosis or treatment. If symptoms are severe or worsening, seek appropriate medical care promptly.

  • What Should I Bring to an Orthopaedic Appointment?

    What Should I Bring to an Orthopaedic Appointment?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Prepare without feeling overwhelmed

    A useful appointment does not require a perfect folder of documents. Bring what you already have, make a few simple notes and be ready to describe how the problem affects everyday movement.

    Clinical consultation illustration for preparing for an orthopaedic appointment

    Short answer

    The most helpful items are your identification and appointment documents, a current medication list, relevant medical information, previous scans or reports and a short symptom timeline. A written question list can make the conversation easier. Missing documents should not delay urgent care.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the assessment and treatment pathway before an individual consultation.

    Key takeaways

    EssentialIdentification, appointment or referral documents and a current medicine list.
    Very helpfulPrevious images, radiology reports, operation notes and a short symptom timeline.
    PersonalYour activity goals and two or three questions you most want answered.
    Do not delayMissing paperwork should never delay urgent assessment for a serious injury or red flag.

    Bring existing scans and reports when available

    Previous X-rays, MRI scans, CT scans, discharge summaries, operative notes and physiotherapy records can provide useful context. If the images are on a disc, USB drive or patient portal, check with the hospital beforehand to find out which formats the clinic can access safely.

    A written radiology report is useful, but the actual images may also matter. Do not send medical documents through an unconfirmed email address or messaging channel. Ask the clinic for the approved way to share them.

    Prepare a clear medication and health summary

    List prescription medicines, over-the-counter pain relief, supplements and known allergies. Include the dose if you know it. Mention conditions such as diabetes, heart or kidney disease, previous blood clots, bleeding concerns and previous problems with anaesthesia, because these can influence investigations and treatment decisions.

    Do not stop prescribed medication before the appointment unless the clinician responsible for it has told you to do so. The first consultation is a chance to review the information and decide what, if anything, needs to change.

    Write a short symptom timeline

    You do not need a long diary. Note when the problem started, whether it followed a fall or twist, what the pain feels like and which movements are difficult. Include swelling, stiffness, weakness, locking, giving way, numbness or changes in walking if present.

    It also helps to say what you have already tried, such as rest, medication, physiotherapy, bracing or activity changes, and whether any of these made a difference.

    Choose the questions that matter most

    Appointments can feel busy, so write down your main concerns. Useful questions include: What might be causing this? Do I need further tests? What options can we try first? What are the benefits and limitations? What symptoms should make me seek help sooner?

    If there are several options, ask how they relate to your work, caregiving, sport, prayer, travel or other priorities. A good plan should be understandable and realistic for your life.

    What clinical guidance supports

    The AAOS visit guide recommends bringing relevant medical records, imaging and a medication list. These are useful because they reduce guesswork and help avoid repeating tests that may already answer the clinical question.

    The NHS question-planning guide suggests writing down your main concerns and checking that you understand the next steps. Preparation is not about impressing the doctor; it is about protecting the questions that matter to you.

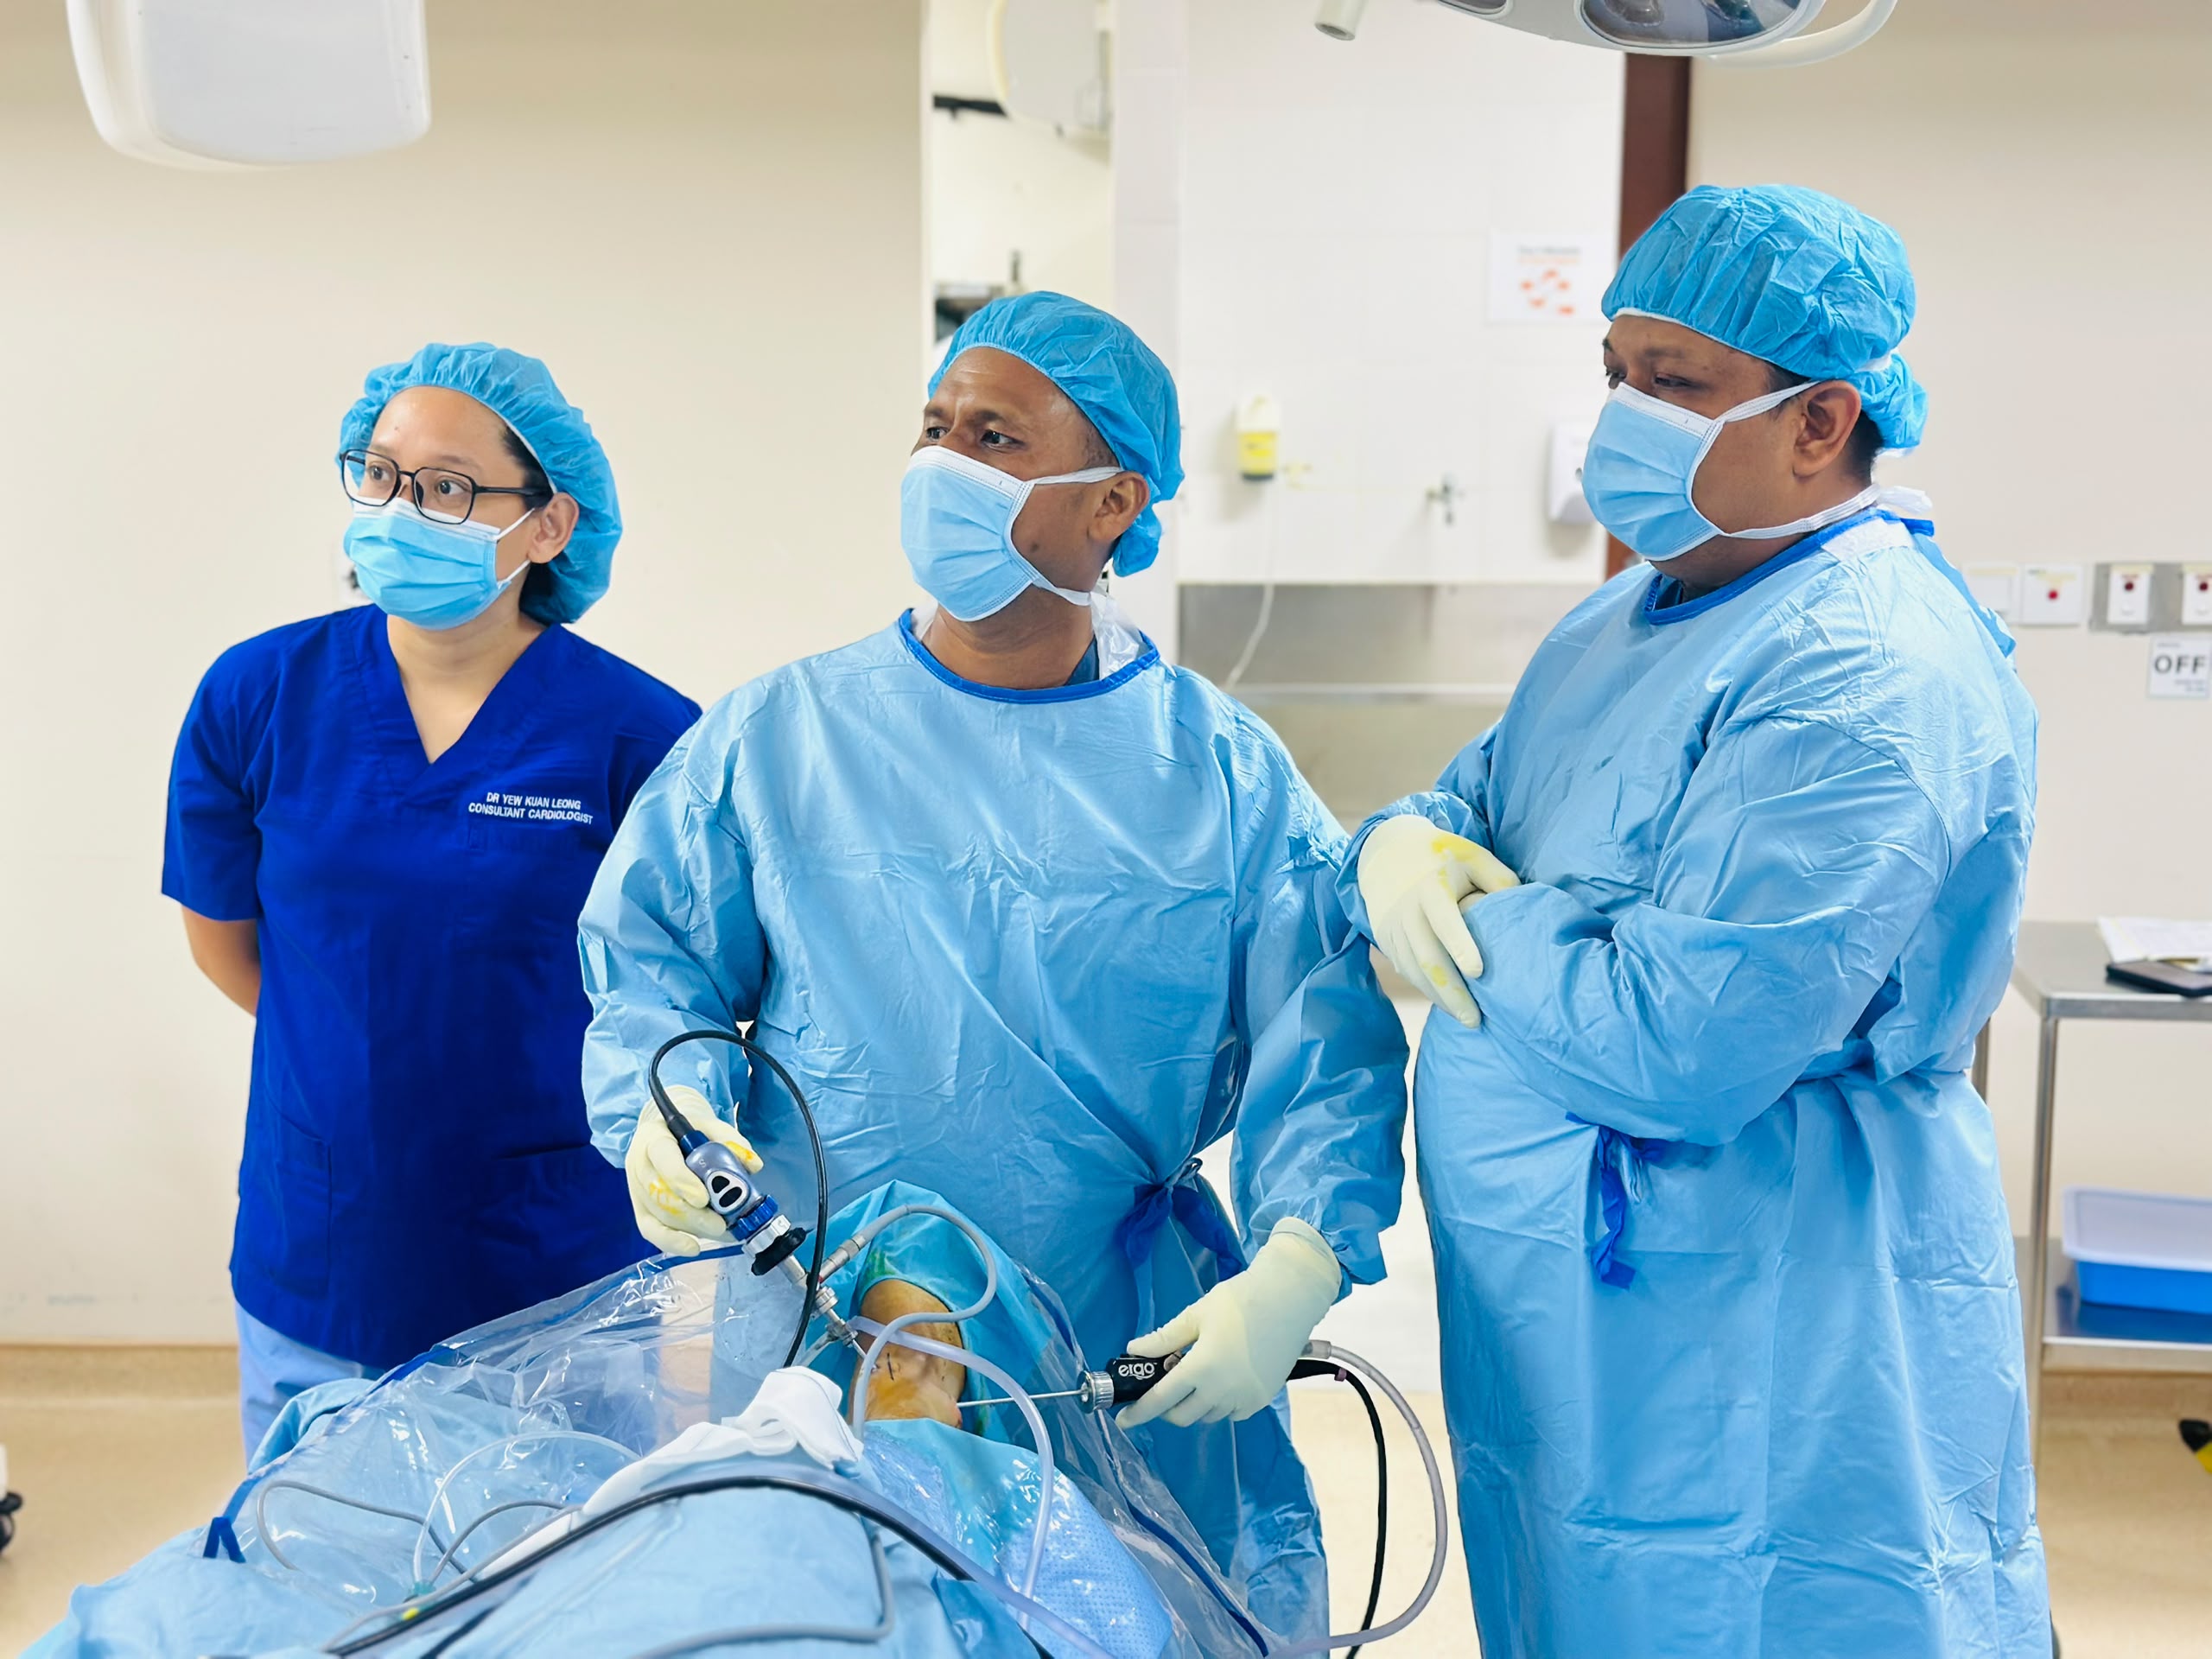
    Dr Shaharil discussing orthopaedic care in a clinical setting
    Bring your questions and existing records so the discussion can focus on a safe, practical next step.

    Build a one-page symptom timeline

    Write when the problem started, whether it followed an injury and how it has changed. Add the activities now limited—walking distance, stairs, kneeling, lifting, work, sleep or sport. Include episodes of swelling, locking, catching, instability, fever, numbness or weakness.

    Keep the timeline short. Exact dates are useful when you know them, but an honest sequence such as ‘started three months ago, worsened after a fall last month’ is better than guessing. Photos of visible swelling or bruising can also help if the appearance changes before the appointment.

    Bring images as well as reports when possible

    A radiology report summarises an interpretation, while the actual X-ray or MRI images allow the orthopaedic surgeon to review the anatomy in the context of your symptoms. Bring the disc, access instructions or digital files if the hospital gave them to you.

    Also bring previous operation notes, implant information, rehabilitation records and relevant blood-test results when available. Do not repeat tests just to make the folder look complete; the clinician can decide what is still needed.

    Prepare for a decision, not only a diagnosis

    List treatments already tried, how long you tried them and what happened. This includes physiotherapy, braces, injections, medicines, activity changes and previous procedures. ‘Did not work’ is more useful when paired with the dose, duration or specific limitation.

    Choose two or three questions: What is the most likely cause? What else could it be? What are my options? What should improve, by when? What symptoms should prompt earlier review? A family member may help you listen and take notes if clinic policy allows.

    How I turn uncertainty into a staged plan

    I usually organise the next step around three questions: what is safe to do now, what missing information would genuinely change treatment, and what development would make us revise the plan. The first step may be activity adjustment, diagnosis-specific rehabilitation, symptom relief or a targeted test. It should be proportionate to both the level of risk and the amount of function you have lost.

    Every plan also needs a review point. We should agree on the change we hope to see, a reasonable timescale and the findings that would mean the strategy is not enough. This avoids waiting indefinitely without direction and also avoids escalating to an invasive treatment before the diagnosis, alternatives and goals are clear.

    Personal factors that can change the recommendation

    Two people with similar scan findings may reasonably choose different plans. Work demands, caregiving, previous injuries, other health conditions, medicines, sport, sleep, willingness to complete rehabilitation and the movement you need to regain can all change the balance of benefit and burden.

    Tell the clinician about diabetes, heart, kidney or stomach problems, blood-thinning medicine, allergies, infection history, pregnancy where relevant, and previous operations or implants. These details do not automatically rule treatment in or out, but they can change medication safety, test selection, procedural risk, preparation and recovery planning.

    Dr Shaharil, Consultant Orthopaedic and Trauma Surgeon in Seremban
    A consultation should connect the clinical findings with the movement and daily activities that matter to you.

    Appointment-day checklist

    • Identification, referral letter and insurance or guarantee-letter documents if applicable.
    • Medication and allergy list.
    • Existing scans, reports and previous treatment notes.
    • Comfortable clothing that allows the affected area to be examined where practical.
    • A short symptom timeline and your most important questions.

    When to seek urgent care

    Do not wait for a routine appointment if you have had a major injury with deformity, an open wound, severe uncontrolled pain, loss of feeling, a cold or pale limb, or inability to move or bear weight. Seek urgent or emergency assessment.

    Frequently asked questions

    What if I have no scans?

    You can still arrange an assessment. After listening and examining you, the clinician can explain whether imaging would be useful.

    Should I stop pain medication before the visit?

    Do not stop prescribed medication unless the responsible clinician tells you to. Bring an accurate list and explain what you have taken.

    Can I show photos of swelling?

    A dated photograph may help show intermittent swelling or bruising that is not present during the visit, but it does not replace examination.

    Can the cause of pain be diagnosed from symptoms alone?

    Symptoms are important, but similar symptoms can arise from different structures or conditions. A diagnosis may require a focused examination and, only when it will change management, an appropriate investigation.

    Should I stop all activity until I am assessed?

    Not automatically. Avoid movements that cause sharp pain, repeated giving way or clear worsening, but complete rest can sometimes increase stiffness and weakness. The safe level of activity depends on the cause and severity.

    Can I take pain medicine before the appointment?

    Do not start, stop or change medication solely because of this article. Ask a doctor or pharmacist what is safe for you, especially if you have kidney, stomach, liver or heart problems, take blood thinners, are pregnant, or use other medicines.

    What if my scan looks normal but I still have pain?

    A scan is one part of assessment. Some painful problems are diagnosed mainly from the history and examination, and some scan findings do not explain the symptoms. Persistent functional difficulty still deserves a clinical review.

    What should I monitor before follow-up?

    Note pain triggers, swelling, sleep disturbance, walking tolerance, work or sport limitations, episodes of locking or giving way, and whether the agreed plan is helping. This gives the follow-up visit useful information.

    Conclusion

    Bring what you have, not what you think a perfect patient should have. A clear symptom story, medicine list, existing scans and your priorities give us a strong starting point—and missing documents can be filled in later when clinically necessary.

    Medical references

    1. AAOS OrthoInfo — Your Visit With an Orthopaedic Surgeon
    2. NHS — What to Ask Your Doctor or Other Healthcare Professional
    3. NICE — Shared Decision Making
    4. General Medical Council — The seven principles of decision making and consent
    5. NHS — Joint pain

    About Dr Shaharil

    Dr Shaharil is a Consultant Orthopaedic & Trauma Surgeon practising at CMH Specialist Hospital in Seremban. Learn more about Dr Shaharil.

    Let’s begin with a clear conversation.

    Tell the clinic what hurts, when it began and what movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical assessment, diagnosis or treatment. If symptoms are severe or worsening, seek appropriate medical care promptly.

  • What Happens During an Orthopaedic Consultation?

    What Happens During an Orthopaedic Consultation?

    Written by Dr ShaharilConsultant Orthopaedic & Trauma Surgeon at CMH Specialist Hospital, Seremban. View Dr Shaharil’s profile.

    Your first orthopaedic visit

    You do not need to arrive with the correct diagnosis or the perfect medical words. An orthopaedic consultation starts with what you feel, what has changed and what you would like to do comfortably again.

    Clinical illustration representing an orthopaedic consultation and assessment

    Short answer

    A first orthopaedic consultation usually includes a conversation about your symptoms and health, a focused physical examination, a review of any existing scans or reports and a discussion of sensible next steps. A scan or operation is not automatic. The plan depends on what the history and examination show.

    This guide is provided by Dr Shaharil Orthopedic Specialist Clinic Seremban to help patients understand the assessment and treatment pathway before an individual consultation.

    Key takeaways

    First stepYour history and daily limitations guide the consultation.
    ExaminationMovement, strength, tenderness, stability and nearby joints may be checked.
    TestsAn X-ray or MRI is requested only when it can answer a useful clinical question.
    OutcomeYou should understand the working diagnosis, uncertainties, options and follow-up.

    The consultation starts with your story

    The first part is often the most useful: explaining what has changed. You may be asked when the problem began, whether there was an injury, where the discomfort is felt and which activities have become difficult. Details such as pain at night, swelling, stiffness, weakness, clicking or a feeling that a joint may give way can help build the clinical picture.

    It is also useful to explain what you hope to return to. For one person that may be walking to the shops; for another it may be kneeling for prayer, working safely, caring for family or returning to sport. Treatment decisions make more sense when they are connected to your own goals.

    A focused examination follows

    The examination is shaped by the problem rather than being exactly the same for everyone. It may include looking at the painful area, checking swelling or tenderness and assessing movement, strength, stability, alignment, walking or the function of nearby joints.

    Tell the doctor if a movement is painful or if you feel unsafe performing it. The aim is not to push through severe pain. The examination helps match what you describe with clinical findings and decide whether another test would add useful information.

    Scans are used when they can answer a clinical question

    Bring previous X-rays, MRI scans and reports if you have them. They may prevent unnecessary repetition and make it easier to compare changes over time. If you do not have scans, that should not stop you from arranging an assessment.

    Not every painful joint needs immediate imaging. An X-ray, MRI, ultrasound or other test is chosen according to the suspected problem and the question the clinician needs to answer. The findings still need to be considered alongside your symptoms and examination.

    You should leave with a clearer next step

    The next step might include advice, activity modification, medication discussion, rehabilitation, further investigation, monitoring or a procedure. Seeing an orthopaedic surgeon does not mean that surgery has already been decided.

    Ask what the likely problem is, what remains uncertain, what options are available and what should happen if the symptoms improve or worsen. Shared decision making means considering the clinical evidence together with the benefits, limitations and consequences that matter to you.

    What clinical guidance supports

    The AAOS patient guide to an orthopaedic visit describes history, examination and review of investigations as connected parts of the assessment—not separate boxes to tick.

    Good decisions also require a genuine conversation. NICE shared decision-making guidance and the GMC principles of consent emphasise discussing reasonable options, benefits, harms and what matters to the individual patient.

    Dr Shaharil, Consultant Orthopaedic and Trauma Surgeon in Seremban
    A consultation should connect the clinical findings with the movement and daily activities that matter to you.

    What the assessment can—and cannot—tell us

    A consultation may identify a clear diagnosis immediately, but sometimes the safest conclusion is a working diagnosis with a staged plan. Early symptoms can overlap, and a single examination finding rarely tells the whole story. I would rather explain what is known, what remains uncertain and how we will test that uncertainty than offer false certainty.

    Your age, occupation, previous injuries, other medical conditions and activity goals can change the meaning of the same symptom. For example, clicking without pain may be less concerning than a new painful catch after a twisting injury. The context determines whether observation, rehabilitation, imaging or another step is reasonable.

    How treatment options are weighed

    Treatment can range from education and activity adjustment to physiotherapy, medicines, injections or surgery. The right sequence depends on the likely diagnosis, severity, duration, functional loss, previous treatment and your preferences. An option is not automatically suitable simply because it exists.

    For every proposed step, ask what it is meant to achieve, how long a fair trial should take, the important risks, what the alternative is and what would make us reconsider. This turns a list of treatments into an accountable care plan.

    What should happen after the visit

    Before leaving, make sure you know whether you can continue work, exercise, driving or sport; whether any movement should be modified; and when review is needed. If a test is arranged, clarify who will discuss the result and whether it changes the plan.

    Seek earlier review if pain or swelling escalates, function deteriorates, a joint repeatedly gives way or new numbness or weakness appears. A plan should have a review point rather than leaving you unsure how long to wait.

    How I turn uncertainty into a staged plan

    I usually organise the next step around three questions: what is safe to do now, what missing information would genuinely change treatment, and what development would make us revise the plan. The first step may be activity adjustment, diagnosis-specific rehabilitation, symptom relief or a targeted test. It should be proportionate to both the level of risk and the amount of function you have lost.

    Every plan also needs a review point. We should agree on the change we hope to see, a reasonable timescale and the findings that would mean the strategy is not enough. This avoids waiting indefinitely without direction and also avoids escalating to an invasive treatment before the diagnosis, alternatives and goals are clear.

    Personal factors that can change the recommendation

    Two people with similar scan findings may reasonably choose different plans. Work demands, caregiving, previous injuries, other health conditions, medicines, sport, sleep, willingness to complete rehabilitation and the movement you need to regain can all change the balance of benefit and burden.

    Tell the clinician about diabetes, heart, kidney or stomach problems, blood-thinning medicine, allergies, infection history, pregnancy where relevant, and previous operations or implants. These details do not automatically rule treatment in or out, but they can change medication safety, test selection, procedural risk, preparation and recovery planning.

    Dr Shaharil discussing orthopaedic care in a clinical setting
    Bring your questions and existing records so the discussion can focus on a safe, practical next step.

    A simple way to prepare

    • Note when the problem began and what makes it better or worse.
    • Bring your medication list and relevant medical conditions.
    • Bring available X-rays, MRI scans, reports or discharge summaries.
    • Write down two or three questions you do not want to forget.

    When to seek urgent care

    Seek urgent or emergency assessment after a major injury if a limb looks deformed, there is an open wound over a possible fracture, pain is severe and uncontrolled, you cannot use the limb, or it becomes pale, cold or numb. A hot, red and very swollen joint with fever or feeling unwell also requires urgent medical attention.

    Frequently asked questions

    Will I need a scan at the first appointment?

    Not necessarily. The need for imaging depends on your symptoms, examination and any previous results. The reason for a recommended scan should be explained.

    Does an orthopaedic consultation always lead to surgery?

    No. Orthopaedic surgeons also diagnose conditions and provide non-surgical treatment planning. Surgery is discussed only when it is clinically appropriate.

    Can I bring someone with me?

    If hospital policy allows, a family member or trusted person may help you remember information and ask questions. Confirm current arrangements with the clinic before attending.

    Can an orthopaedic problem be diagnosed from symptoms alone?

    Symptoms are important, but similar symptoms can arise from different structures or conditions. A diagnosis may require a focused examination and, only when it will change management, an appropriate investigation.

    Should I stop all activity until I am assessed?

    Not automatically. Avoid movements that cause sharp pain, repeated giving way or clear worsening, but complete rest can sometimes increase stiffness and weakness. The safe level of activity depends on the cause and severity.

    Can I take pain medicine before the appointment?

    Do not start, stop or change medication solely because of this article. Ask a doctor or pharmacist what is safe for you, especially if you have kidney, stomach, liver or heart problems, take blood thinners, are pregnant, or use other medicines.

    What if my scan looks normal but I still have pain?

    A scan is one part of assessment. Some painful problems are diagnosed mainly from the history and examination, and some scan findings do not explain the symptoms. Persistent functional difficulty still deserves a clinical review.

    What should I monitor before follow-up?

    Note pain triggers, swelling, sleep disturbance, walking tolerance, work or sport limitations, episodes of locking or giving way, and whether the agreed plan is helping. This gives the follow-up visit useful information.

    Conclusion

    A good orthopaedic consultation should leave you more informed, not more pressured. My aim is to understand the movement you have lost, explain the likely cause in plain language and agree on the safest proportionate next step with you.

    Medical references

    1. AAOS OrthoInfo — Your Visit With an Orthopaedic Surgeon
    2. NHS — What to Ask Your Doctor or Other Healthcare Professional
    3. NICE — Shared Decision Making
    4. General Medical Council — The seven principles of decision making and consent
    5. NHS — Joint pain

    About Dr Shaharil

    Dr Shaharil is a Consultant Orthopaedic & Trauma Surgeon practising at CMH Specialist Hospital in Seremban. Learn more about Dr Shaharil.

    Let’s begin with a clear conversation.

    Tell the clinic what hurts, when it began and what movement has become difficult. The team can help arrange an appointment with Dr Shaharil.

    WhatsApp for an appointment

    This information is general and does not replace an individual medical assessment, diagnosis or treatment. If symptoms are severe or worsening, seek appropriate medical care promptly.